
TRT Results Timeline: What Changes Month by Month
Most men expect testosterone therapy to feel like flipping a switch. It doesn’t, and a realistic TRT results timeline looks nothing like the overnight transformation
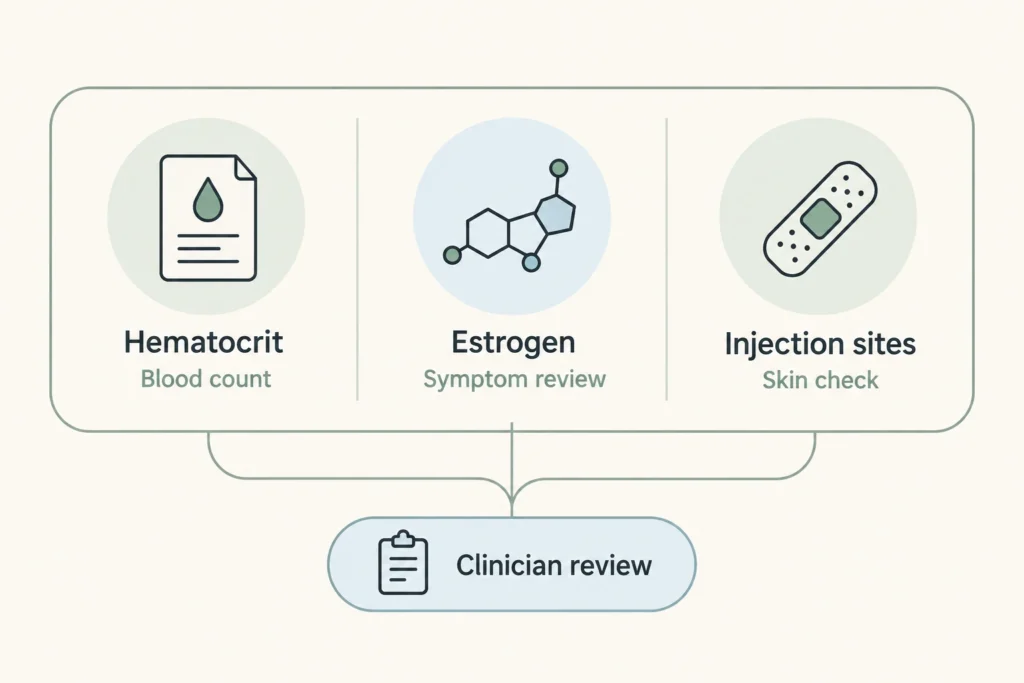
Ask ten men about TRT side effects and you’ll hear ten different fears, most of them wrong. Shrinking testicles, aggression, hair loss, none of these are the things a provider is actually watching your labs for. The two numbers that genuinely require active management are your hematocrit and your estradiol, and the technique that matters most day to day is how you rotate injection sites. Everything else is either rare, manageable, or overstated.
None of this is a reason to treat TRT as risk-free. It’s a reason to be specific about what the real risks are, because vague fear leads to either skipping monitoring that actually matters or panicking over something that doesn’t.

Testosterone therapy can raise hematocrit, the percentage of red blood cells in your blood, because testosterone stimulates red blood cell production. Left unchecked, a hematocrit that climbs too high thickens the blood and raises the risk of clotting. A study following men on testosterone therapy found secondary polycythemia, meaning an abnormally high red blood cell count, was linked to a higher risk of major cardiac events and blood clots in the first year of treatment, which is exactly why hematocrit gets checked before that first year is over, not after.
The management playbook here is well established. A recent narrative review on managing hematocrit during testosterone therapy lays out the standard sequence: baseline hematocrit before starting, recheck at three to six months, then annual monitoring after that, with dose reduction, a change in formulation, or therapeutic blood donation as options if hematocrit climbs too high. Full discontinuation is rarely the first move anymore; it’s the last one, used when the other adjustments haven’t brought the number back down.
Men sometimes ask whether a rising hematocrit means the protocol has failed. It doesn’t. It means the dose or delivery method needs a change, the same way a blood pressure medication gets adjusted rather than abandoned the first time a reading runs high. The Cleveland Clinic’s overview of testosterone replacement therapy frames ongoing lab monitoring as a routine, expected part of treatment rather than a sign something has gone wrong.
Testosterone converts to estradiol in the body through a process called aromatization, and that conversion increases as testosterone levels rise on therapy. A small amount of estradiol is necessary and healthy; too much can cause water retention, mood changes, and breast tenderness, while too little, often from over-aggressive estrogen suppression, can cause joint pain and low libido, working against the exact symptoms TRT is meant to fix.
The goal isn’t zero estradiol. It’s a level appropriate to your testosterone dose, tracked with periodic labs and adjusted individually rather than treated with a blanket rule. Men on higher testosterone doses, or those with more body fat, which increases aromatization, are more likely to need estradiol monitored closely and occasionally managed with a small adjunct medication. This is a conversation to have with your prescribing provider directly, since blanket over-the-counter aromatase suppression without lab guidance is more likely to cause a new problem than fix an existing one.
Site rotation matters more than most men expect. Repeatedly injecting the same spot causes local tissue damage, scarring, and eventually lumps that interfere with absorption, which can make dosing less predictable even when the dose itself hasn’t changed. A simple rotation pattern, alternating between two or more sites and never returning to the same spot within roughly two weeks, prevents most of this.
Technique matters as much as rotation. Correct needle length, angle, and injection speed for your specific protocol, whether subcutaneous or intramuscular, should be demonstrated directly by your provider rather than learned from a video. A provider who reviews your technique at your first few visits, not just your labs, is catching the kind of preventable problem that never shows up as a symptom until it already has.
This question has genuinely changed over the past two years. Older testosterone product labels carried a boxed warning about cardiovascular risk, based largely on smaller and less definitive earlier studies. That changed with the TRAVERSE trial, a large randomized study specifically designed to answer this question in men with existing or high cardiovascular risk, which found testosterone replacement therapy was not associated with an increase in major adverse cardiac events compared with placebo, while also flagging a higher rate of atrial fibrillation, blood clots, and fractures in the testosterone group.
That data directly changed the regulatory picture. The FDA’s February 2025 class-wide labeling update removed the boxed cardiovascular warning from testosterone products, citing the TRAVERSE results and additional postmarket studies, while adding a new warning about increased blood pressure across the entire product class. Recent FDA TRT stance changes and what they mean for you covers this shift in more depth, including what it does and doesn’t change about who’s a good candidate for treatment.
Acne, oily skin, and fluid retention show up in a minority of men, usually early in treatment, and typically settle once the dose is dialed in. Sleep apnea deserves a direct mention: testosterone therapy can worsen existing, undiagnosed sleep apnea, which is one reason a symptom review at follow-up visits includes sleep quality and not just energy level. The Endocrine Society’s clinical practice guideline on testosterone therapy specifically recommends evaluating for sleep apnea symptoms as part of routine monitoring, not just at intake.
Fertility effects, covered in more depth in enclomiphene vs. TRT, belong on this list too. TRT commonly reduces sperm production while a man is on it, which matters most for men who haven’t finished building their family. None of these effects are reasons to avoid treatment outright; they’re reasons the monitoring schedule exists in the first place, and why a provider conversation before starting covers more ground than a product label ever could.
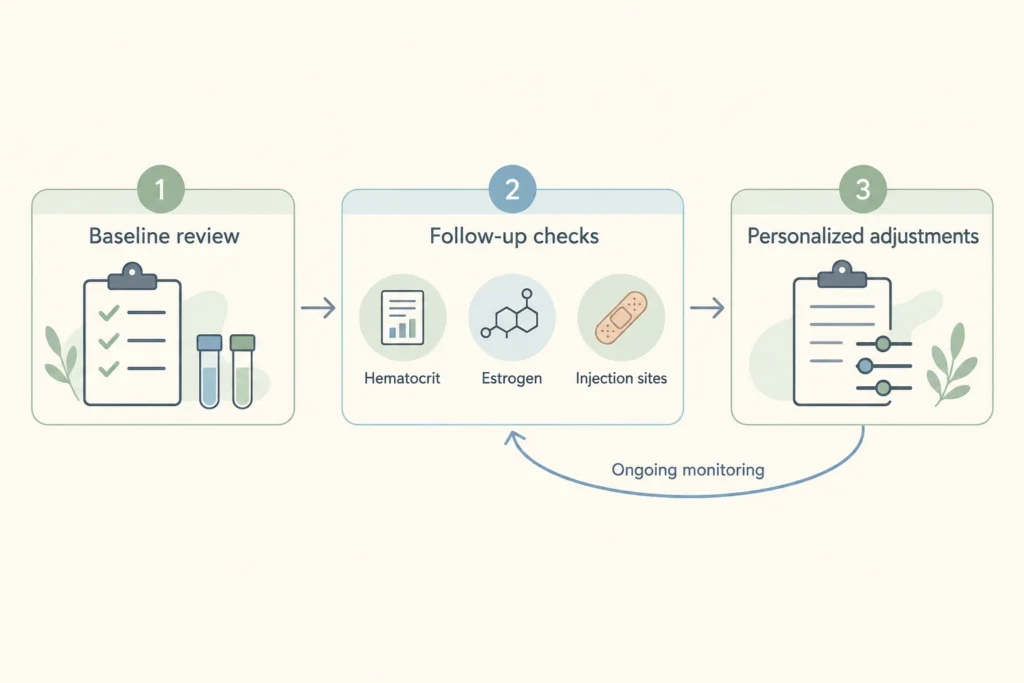
At Body Works, side effect management isn’t a reaction to a problem; it’s built into the protocol from day one. Every man starting testosterone therapy in Franklin, TN or Nolensville, TN gets a baseline hematocrit and estradiol drawn before the first dose, a recheck built into the schedule rather than left to the patient to request, and hands-on injection technique review at the visits where problems are easiest to prevent. What physician-supervised treatment looks like covers this monitoring schedule as part of the full process.
Men who are weighing TRT against an alternative because of these monitoring requirements should also look at enclomiphene vs. TRT, since the two options carry different side effect profiles entirely. And if you’re already on TRT and wondering whether what you’re feeling at a given point matches what’s expected, the TRT results timeline lays out what changes month by month.
Schedule a Free Consultation to talk through your specific risk factors before starting, or to review your current monitoring schedule if you’re already on treatment.
Medically reviewed by Dr. Donald Vollmer, MD
Managing Physician, Body Works TN
Most men expect testosterone therapy to feel like flipping a switch. It doesn’t, and a realistic TRT results timeline looks nothing like the overnight transformation
Two men walk into the same clinic with nearly identical lab results: both have low testosterone, both are in their late 30s, both still want

He’s 38, sleeping seven hours a night, still hitting the gym three times a week, and he still feels like he’s dragging a weighted sled

A 42-year-old man gets his testosterone checked, and the lab report comes back with a single word next to the number: “normal.” He still feels

A lot of what passes for testosterone replacement therapy in Franklin, TN and nationwide in 2026 is a questionnaire, a card swipe, and a prescription
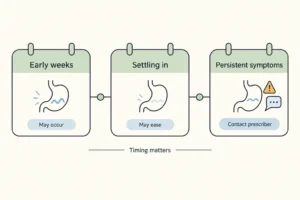
A symptom that is completely normal in week two can be a reason to call your prescriber in week fourteen. Nausea right after a dose
See Body Works first in your Google results.
