

MOTS-c: The Mitochondrial Peptide for Metabolism and Endurance
For decades, the DNA inside your mitochondria was treated as a parts list for one job: energy production, nothing else. Then researchers found a 16-amino-acid
Patients starting tirzepatide often expect the first injection to feel like the start of real treatment. It isn’t. The 2.5 mg starting dose is a lead-in step the label says is not intended to produce weight loss on its own, and plenty of new patients spend a full month wondering why nothing seems to be happening.
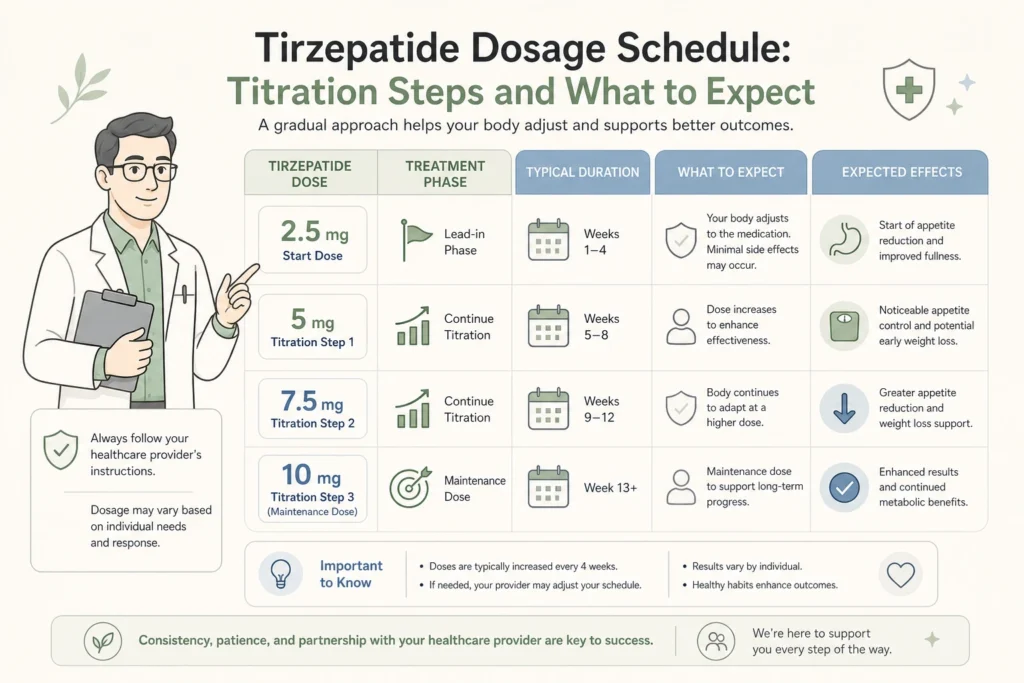
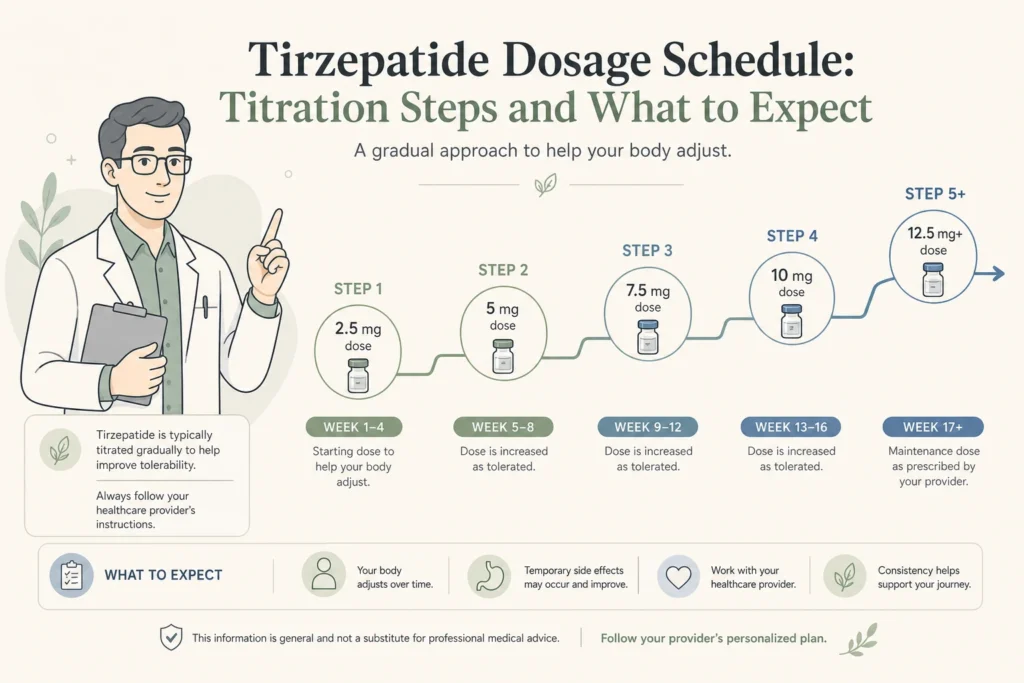
Tirzepatide’s titration schedule moves in 2.5 mg increments, from a 2.5 mg starting dose up to a possible maximum of 15 mg, with at least four weeks required between any increase. Unlike some GLP-1 schedules, most of those increases are optional rather than mandatory. Every patient starts the same way, but where they land depends on response and tolerability, not a fixed finish line printed on the label. That’s exactly what Body Works physicians in Nolensville, TN and Franklin, TN reassess at every follow-up, comparing weight trend and side effects against the current dose before ever discussing the next one.
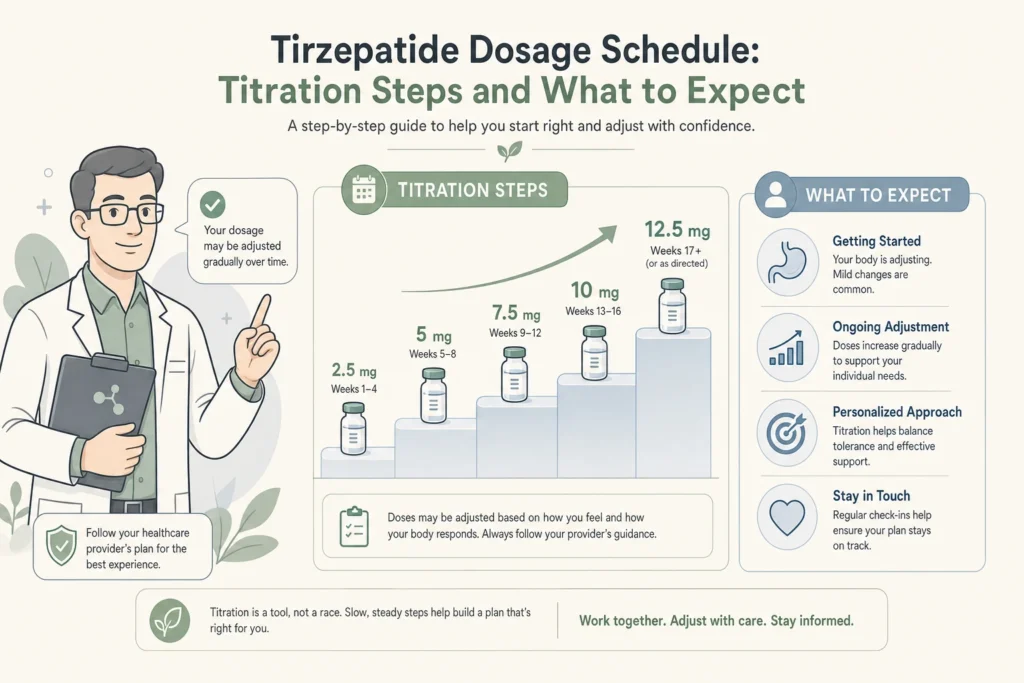
Tirzepatide has six possible dose levels between the starting point and the labeled maximum, but only the first increase is fixed on the label. Everything after 5 mg is an “if needed” decision a prescriber makes based on how much additional weight reduction or glycemic control the current dose is still producing.
| Step | Earliest week | Dose | Status |
|---|---|---|---|
| 1 | 1 | 2.5 mg weekly | Lead-in dose, not intended to be therapeutic |
| 2 | 5 | 5 mg weekly | First dose with a treatment effect |
| 3 | 9 | 7.5 mg weekly | Optional increase |
| 4 | 13 | 10 mg weekly | Optional increase |
| 5 | 17 | 12.5 mg weekly | Optional increase |
| 6 | 21 | 15 mg weekly | Maximum labeled dose |
These steps come from the FDA-approved prescribing information for tirzepatide, which requires at least four weeks at a dose before any further increase. A prescriber sets your actual pace and ceiling based on your response and tolerability, not this table.
The 2.5 mg starting dose exists purely to reduce nausea and vomiting before the drug’s real GIP and GLP-1 effects begin at 5 mg. Tirzepatide is a dual agonist, meaning it activates two gut hormone receptors instead of one, and the combined effect on appetite and gastric emptying is stronger than semaglutide’s at a comparable point in titration.
That extra strength is also why the lead-in step exists at all. Starting straight at 5 mg produces far more gastrointestinal side effects in most patients than easing in at half that dose for a month first. The FDA label reports constipation in 17% of patients at the 5 mg dose, 14% at 10 mg, and 11% at 15 mg, against 5% on placebo, a rate that actually trends down at higher doses once the body has adapted through the lower steps. Four weeks is enough time for the gut to adjust before the medication is asked to do its actual job.
No. Many patients plateau their titration well below 15 mg once their weight loss and appetite control are meeting goals, because higher doses do not automatically mean better results for every patient, only the option of them. In the SURMOUNT-1 trial published in the New England Journal of Medicine, the three tested maintenance doses, 5 mg, 10 mg, and 15 mg, produced average weight reductions of 16.0%, 21.4%, and 22.5% respectively at 72 weeks, meaningful results at every level tested, not just the top one.
A prescriber who keeps a patient at 10 mg instead of pushing toward 15 mg isn’t underdosing them. If the current dose is producing steady progress with tolerable side effects, there’s often no clinical reason to climb further. Increases are meant to answer a specific question, is more dose needed, not to fill out the highest number on the label.

Semaglutide’s titration is more rigid: five fixed steps from 0.25 mg to a single 2.4 mg maintenance dose, each held for four weeks regardless of response, as laid out in the FDA-approved prescribing information for semaglutide. Tirzepatide’s ladder has more optional stops but also more room to stay at a lower, better-tolerated dose if it’s already working. In the STEP 1 trial, semaglutide’s maintenance dose produced 14.9% average weight loss at 68 weeks, below tirzepatide’s dual-hormone effect at comparable doses.
Neither schedule is objectively faster since both take roughly four months minimum to reach a standard treatment dose. The choice between them usually comes down to how a patient’s body responds to each mechanism, not the calendar. In the STEP 1 trial published in the New England Journal of Medicine, semaglutide patients kept losing weight through the full 68-week study, and tirzepatide showed the same pattern through 72 weeks in SURMOUNT-1, so neither medication’s titration schedule is really about speed. It’s about finding the dose your body tolerates well enough to sustain long-term treatment. Our full semaglutide dosage schedule guide lays out that comparison in detail, and both medications are available through physician-supervised programs at tirzepatide therapy and semaglutide therapy.
Nausea, reduced appetite, and occasional constipation tend to reappear briefly after every dose increase, then settle within a week or two, a pattern that repeats at each of the six steps. That repeating pattern is normal and expected. What isn’t normal is severe abdominal pain, persistent vomiting, or an inability to keep fluids down, all of which warrant a same-day call to your prescriber rather than waiting it out. A full breakdown of what’s typical at each week of treatment, and what counts as a red flag, is in our guide to GLP-1 side effects by week.
Injection technique matters more as the dose climbs. According to the tirzepatide injection instructions published by MedlinePlus, the medication is injected into the abdomen, thigh, or upper arm, and the site should rotate with every dose. The same source notes that a missed dose can still be taken up to four days late. Beyond that window, skip it and resume the normal weekly schedule rather than doubling up. That full process, including what changes at higher doses, is covered in how to inject semaglutide and tirzepatide. For a deeper look at what results typically look like at each dose level, see our tirzepatide deep dive on dosing and results.
The most common question our clinical team hears during a tirzepatide follow-up isn’t “when do I go up,” it’s “do I need to.” That’s a deliberate shift from how most patients expect titration to work, and it’s why Body Works reviews weight trend, appetite control, and side effects at every visit before deciding whether the next step is worth taking.
Whether you’re about to start tirzepatide or you’re mid-titration and unsure whether to increase, our physician-supervised teams in Franklin and Nolensville build the ladder around your response, not a fixed chart. Schedule a Free Consultation to get started.
Medically reviewed by Dr. Donald Vollmer, MD
Managing Physician, Body Works TN
For decades, the DNA inside your mitochondria was treated as a parts list for one job: energy production, nothing else. Then researchers found a 16-amino-acid
Search “peptide therapy near me” and the results mix licensed medical clinics with websites selling research-use-only vials to your front door, no prescription, no bloodwork,
Search “BPC-157 TB-500 stack” and the forums all say the same thing: pair them, because one heals the tissue and the other helps cells get

A single glass of wine that never used to bother anyone can suddenly cause real nausea a few months into semaglutide or tirzepatide treatment. Patients
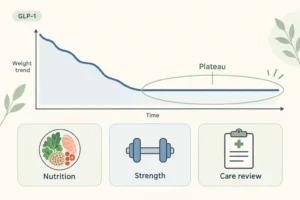
Three months of steady loss, then two weeks of nothing, then a patient calls certain the medication stopped working. It didn’t. A GLP-1 plateau is

Ask ten men about TRT side effects and you’ll hear ten different fears, most of them wrong. Shrinking testicles, aggression, hair loss, none of these
See Body Works first in your Google results.
