Testosterone Replacement Therapy in Franklin and Nolensville: What Physician-Supervised Treatment Looks Like

Testosterone Replacement Therapy in Franklin and Nolensville: What Physician-Supervised Treatment Looks Like

October 14, 2026

A lot of what passes for testosterone replacement therapy in Franklin, TN and nationwide in 2026 is a questionnaire, a card swipe, and a prescription mailed to your door, no exam, no repeat labs, no provider who’s actually looked at your bloodwork twice. That model exists because it’s fast and it’s cheap to run. It also means nobody’s watching your hematocrit, nobody’s asking whether your symptoms actually match a hormonal cause, and nobody’s adjusting your dose based on how you’re actually responding.

Physician-supervised TRT looks different, and slower, on purpose. At Body Works, treatment for men in Franklin, TN and Nolensville, TN starts with a real diagnostic workup and stays supervised through every dose adjustment after that. Here’s what that process actually looks like, start to finish.

Illustration of Testosterone Replacement Therapy in Franklin and Nolensville: What Physician-Supervised Treatment Looks Like in a modern medical wellness setting

What Happens at the First TRT Consultation?

The first visit is a conversation before it’s a blood draw. A provider reviews your symptoms against the pattern clinicians actually screen for, since fatigue, low libido, and mood changes overlap with a dozen other conditions and testosterone testing without a symptom match rarely changes anything useful. The low testosterone symptoms checklist covers the specific pattern that pattern-matches to a hormonal cause versus a lifestyle one.

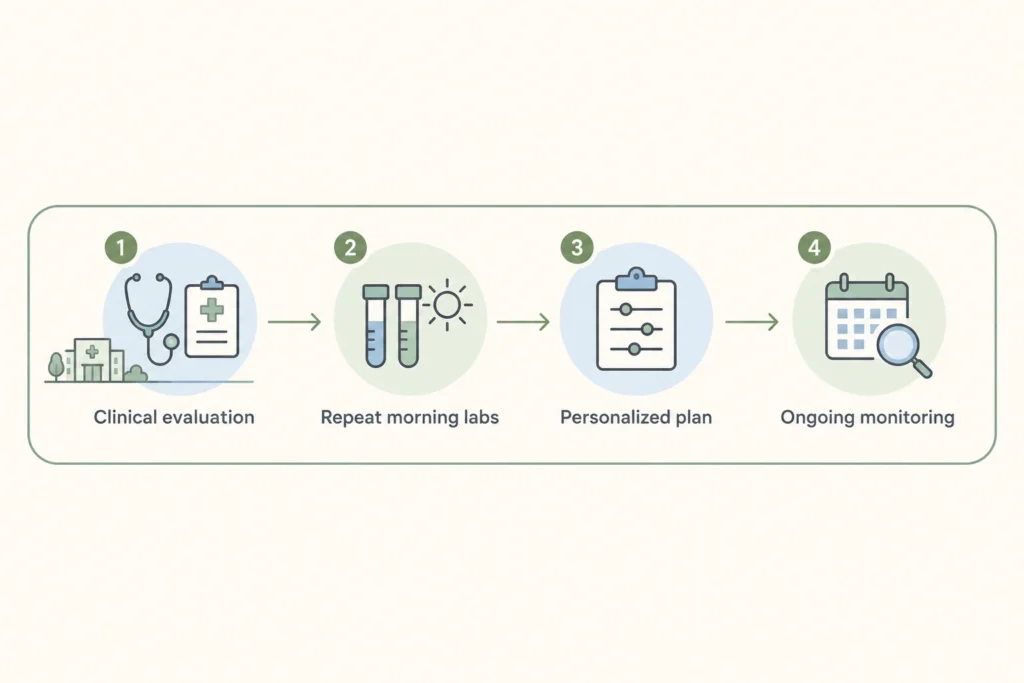
If your symptoms and history support testing, labs come next, timed correctly. The Endocrine Society’s clinical practice guideline on testosterone therapy calls for a fasting morning draw, confirmed by a second separate measurement, before any diagnosis is made. That two-draw standard is the default at Body Works, not an upsell; a single afternoon test is exactly the kind of shortcut that produces a wrong answer in either direction.

How Is a TRT Diagnosis Actually Confirmed?

Diagnosis requires both a confirmed low testosterone level and a symptom pattern that matches it, not one or the other. Testosterone levels by age covers why a single “normal” lab result doesn’t always settle the question, particularly for men whose number sits near a lab’s cutoff or whose free testosterone tells a different story than their total testosterone.

Depending on what the labs show, the diagnosis also determines the treatment options on the table. Men with a healthy testicular signal but low pituitary drive sometimes have a genuine alternative to direct testosterone replacement. Enclomiphene vs. TRT walks through that decision for men where fertility is part of the conversation.

What Does a TRT Protocol Include?

Once a diagnosis is confirmed and treatment is the right call, the protocol covers medication, dose, delivery method, and a monitoring schedule built in from day one, not added later if something goes wrong. The Mayo Clinic’s overview of testosterone therapy notes that delivery options include injections, gels, and pellets, each with different dosing rhythms and different tradeoffs a provider should walk through based on your lifestyle and lab response, not a one-size default.

Baseline hematocrit and estradiol are drawn before the first dose, with a recheck built into the calendar at three to six months and annually after that. TRT side effects and how they’re managed covers exactly what that monitoring catches and what happens if a number runs outside the expected range.
Supporting illustration for Testosterone Replacement Therapy in Franklin and Nolensville: What Physician-Supervised Treatment Looks Like in a modern medical wellness setting

What Should I Expect in the First Few Months?

Results don’t arrive on day one. Most men notice little change in the first two weeks, a real lift in mood, libido, and energy by four to eight weeks, and measurable changes in strength and body composition around the three-month mark, once levels have stabilized and tissue has had time to respond. The full TRT results timeline breaks down what changes at each checkpoint so you know what’s expected and what’s worth flagging to your provider.

Recent regulatory changes are also worth knowing before you start. Testosterone products carried a boxed cardiovascular warning for years; the FDA removed that warning in February 2025 based on large-scale trial data showing no increase in major cardiac events, while adding a new blood pressure warning across the product class. A physician-supervised protocol accounts for both the updated safety picture and the individual monitoring that still matters.

Why Physician Supervision Matters for TRT

A prescription is not the hard part of testosterone therapy. Getting the diagnosis right, catching a hematocrit or estradiol trend before it becomes a problem, and adjusting a protocol based on how an individual man actually responds, that’s the part a ten-minute online intake form cannot do. The Cleveland Clinic’s overview of testosterone replacement therapy describes ongoing lab monitoring and dose adjustment as a routine, expected part of treatment, which only works if a provider is actually reviewing results and adjusting course rather than auto-refilling the same dose indefinitely.

This is also where a diagnostic threshold question matters. Specialty guidelines don’t fully agree on where the biochemical cutoff for low testosterone sits; the American Association of Clinical Endocrinologists’ guideline on hypogonadism in adult men has historically used a different threshold than some other specialty frameworks, which means the same lab number can read differently depending on which guideline a provider follows. Working with a provider who treats the lab value and the symptom pattern together, rather than a number in isolation, is what keeps a diagnosis from becoming a guess.

None of this requires a man to become an expert in endocrinology before his first visit. It’s the reason physician supervision exists in the first place: someone trained to weigh these frameworks against your specific labs and symptoms, rather than applying a single fixed cutoff to every man who walks in the door.

Supporting illustration for Testosterone Replacement Therapy in Franklin and Nolensville: What Physician-Supervised Treatment Looks Like in a modern medical wellness setting

Testosterone Replacement Therapy in Franklin, TN

Body Works’ Franklin location, at 1113 Murfreesboro Rd Suite 307, Franklin, TN 37064, offers the same physician-supervised process described above: symptom review, confirmed diagnostic labs, a tailored protocol, and ongoing monitoring. Learn more about TRT at the Franklin location or call (615) 790-2548 to ask questions before booking.

TRT in Nolensville, TN

Body Works’ Nolensville location, at 210 Burkitt Commons Ave, Nolensville, TN 37135, runs the identical diagnostic and monitoring process for men closer to that side of Williamson County. Learn more about TRT at the Nolensville location or call (615) 941-1000 with questions ahead of your visit.
Supporting illustration for Testosterone Replacement Therapy in Franklin and Nolensville: What Physician-Supervised Treatment Looks Like in a modern medical wellness setting

What to Bring to Your First Visit

Bring any recent lab results, even if they’re from an urgent care visit or a previous provider, along with a specific list of symptoms and how long each has been present. If you’re weighing TRT against a fertility-preserving alternative, come with that priority named upfront, since it changes which labs get ordered on day one rather than after a diagnosis is already set. A current medication list and a rough timeline of when symptoms started are also worth having ready; both shape how a provider reads your first set of labs.

If you’ve already had testosterone checked elsewhere and were told your number was “normal,” bring that result anyway rather than assuming it settles the question. A single number without a repeat draw, without a free testosterone check, and without a symptom conversation attached to it is often an incomplete answer rather than a final one.

Men working with Body Works’ hormone therapy program in Franklin and Nolensville get the same physician-supervised standard regardless of which location is more convenient: confirmed labs before treatment, a real monitoring schedule after it, and a provider who reviews results rather than auto-renewing a prescription.

Schedule a Free Consultation at either location to start with a real conversation, not a questionnaire.

Frequently Asked Questions

No referral is required. A consultation and, if appropriate, diagnostic labs are the starting point for any man considering testosterone therapy.
Confirming a diagnosis typically takes two visits, since guidelines call for a second, separate morning lab draw before treatment starts. This protects against basing treatment on a single unreliable result.
Yes. Both locations offer the same physician-supervised diagnostic and treatment process, so the choice between them typically comes down to which is more convenient for you.
TRT replaces testosterone directly, while enclomiphene stimulates your body to produce more of its own. Which one fits depends on the type of hypogonadism you have and whether preserving fertility is a priority; the full comparison covers both options in detail.
Cost depends on the labs ordered, the protocol chosen, and ongoing monitoring. Body Works is a cash-pay practice, and a free consultation is the fastest way to get exact pricing for your specific situation before anything is prescribed.
The Franklin office is at 1113 Murfreesboro Rd Suite 307, Franklin, TN 37064, reachable at (615) 790-2548. The Nolensville office is at 210 Burkitt Commons Ave, Nolensville, TN 37135, reachable at (615) 941-1000.

Medically reviewed by Dr. Donald Vollmer, MD
Managing Physician, Body Works TN

Browse Our Blog

GLP-1 Side Effects by Week: What Is Normal, What Passes, What to Report

GLP-1 Side Effects by Week: What Is Normal, What Passes, What to Report

October 12, 2026

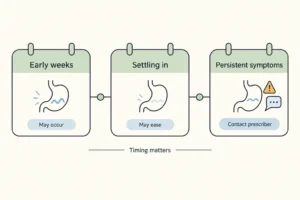
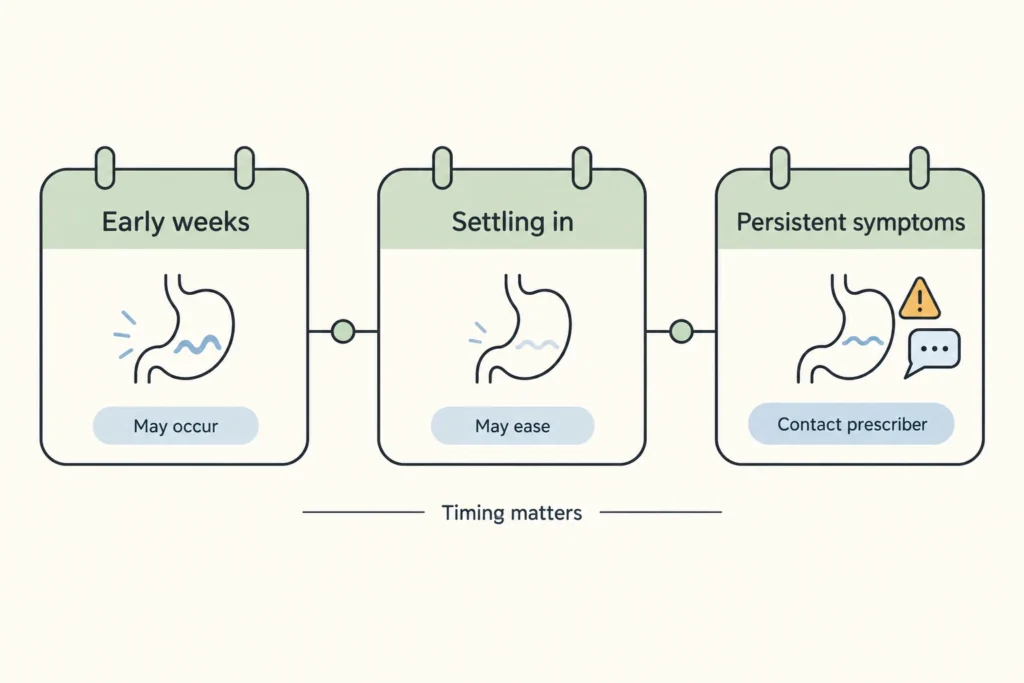
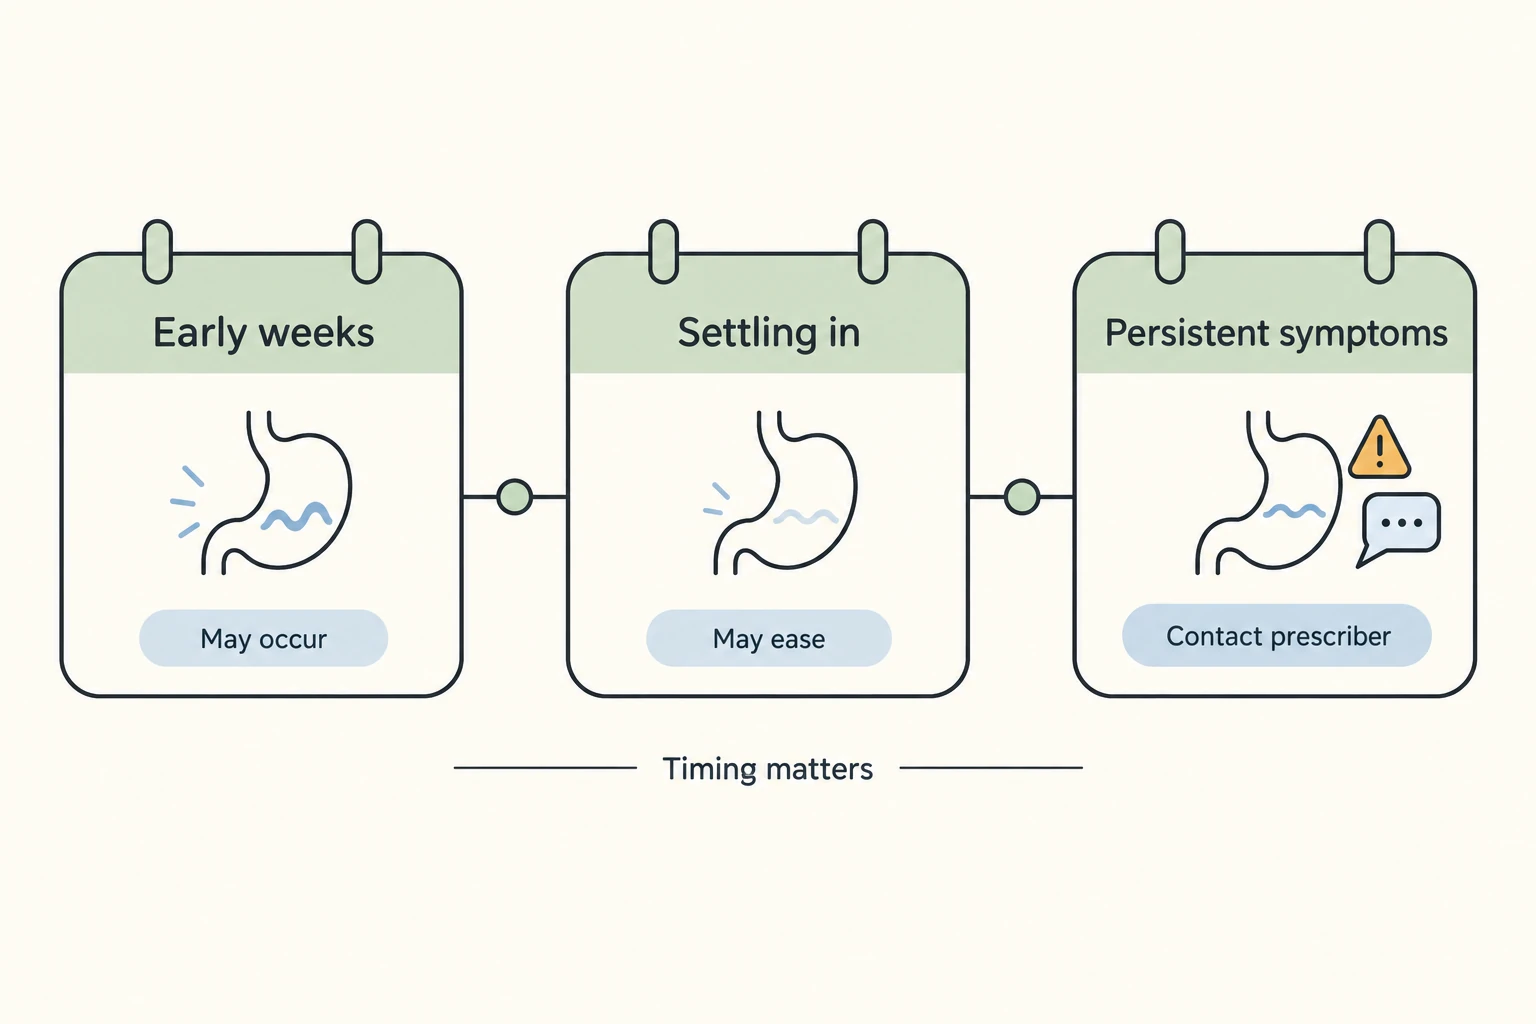
A symptom that is completely normal in week two can be a reason to call your prescriber in week fourteen. Nausea right after a dose increase is expected. The same nausea, unchanged, six weeks after your last increase is not, and treating every GLP-1 side effect as equally routine is how patients miss the ones that actually need attention.

GLP-1 side effects follow the dose, not the calendar: they cluster in the days after each increase, fade before the next one, and mean something different depending on where you are in titration. Semaglutide, tirzepatide, and retatrutide all share this pattern even though their exact rates differ. Body Works physicians in Franklin, TN and Nolensville, TN use that pattern, not just the symptom itself, to tell routine from concerning.

Illustration of GLP-1 Side Effects by Week: What Is Normal, What Passes, What to Report in a modern medical wellness setting

What Is Normal in the First Four Weeks?

Mild nausea, reduced appetite, and occasional loose stool are the most common early effects, and they usually show up within the first few days of the starting dose. The FDA-approved semaglutide label reports nausea in 44% of patients during the trial period, most heavily concentrated in the early weeks, against 16% on placebo.

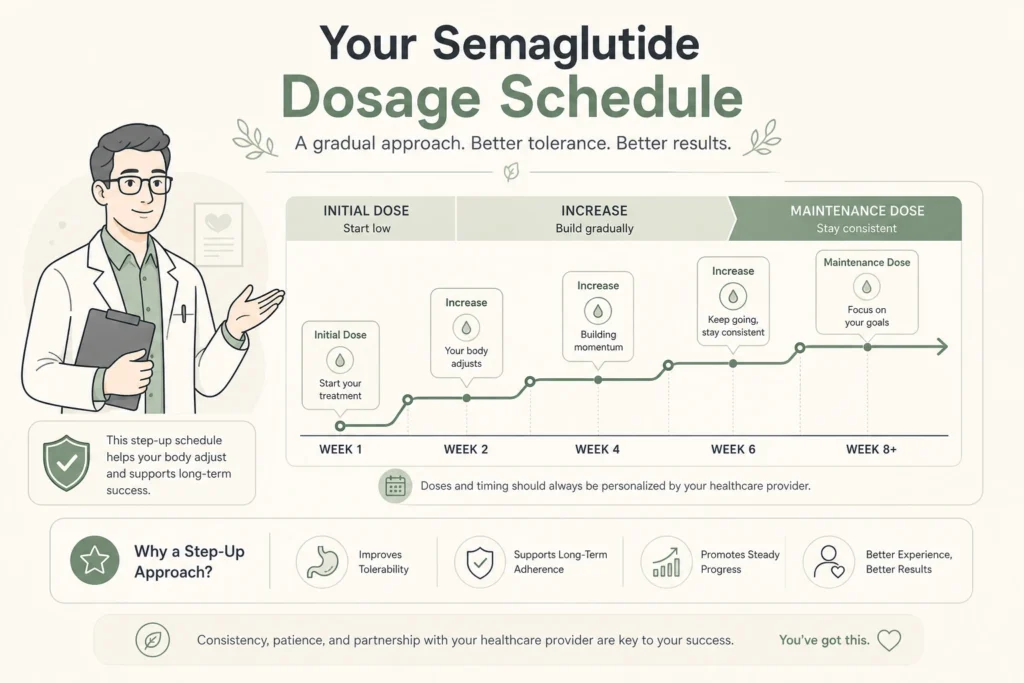
These effects exist because the medication is intentionally slowing digestion and quieting appetite signals, the mechanism doing exactly what it’s supposed to do. Most patients notice symptoms easing within a week of a dose increase, well before the next one arrives a month later. Full details on what to expect at this stage, and how the schedule is built to minimize it, are in our semaglutide dosage schedule guide.

What Changes During Weeks 5 Through 16?

Each dose increase brings a brief return of symptoms, usually milder than the first time, followed by another period of adjustment. Constipation tends to become more prominent in this window as appetite and food volume drop further, appearing in 24% of semaglutide patients per the FDA label, and in 11% to 17% of tirzepatide patients depending on dose according to its own FDA-approved prescribing information.

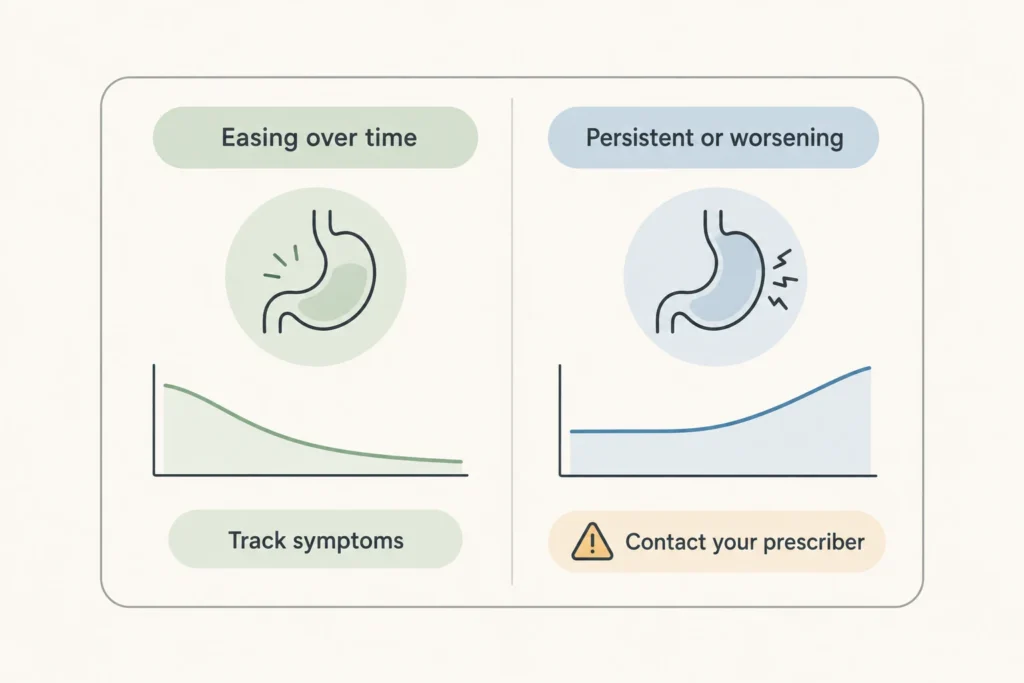
This is also when patients most often ask whether something is wrong because a side effect they’d stopped noticing came back. A returning symptom right after a scheduled dose increase is expected and typically settles within a week or two. The same symptom appearing with no dose change behind it is the pattern that deserves a closer look, covered in the red-flag section below.

Do Semaglutide Side Effects Differ From Tirzepatide's?

Yes, modestly. Semaglutide side effects run somewhat higher for nausea, 44% versus 25% to 29% for tirzepatide depending on dose, while tirzepatide’s dual GLP-1/GIP mechanism produces a comparable or lower gastrointestinal burden at equivalent points in titration. In the STEP 1 trial published in the New England Journal of Medicine, gastrointestinal events were the most common reason for discontinuation, at under 5% of participants. The SURMOUNT-1 trial reported a similarly low discontinuation rate for tirzepatide.

Neither medication’s side-effect profile predicts how well it will work for a given patient. Some people tolerate semaglutide with almost no symptoms and struggle more with tirzepatide, and the reverse happens just as often. Our tirzepatide dosage schedule guide covers what to expect at each of its six possible dose steps.

Supporting illustration for GLP-1 Side Effects by Week: What Is Normal, What Passes, What to Report in a modern medical wellness setting

What About Retatrutide Side Effects?

Retatrutide’s side-effect pattern looks similar to the other two but is documented in trial data only, since it does not yet have an FDA label. In its phase 2 trial published in the New England Journal of Medicine, gastrointestinal events were the most common adverse effect and were clearly dose related, with a lower starting dose reducing their frequency, the same titration logic that governs semaglutide and tirzepatide.

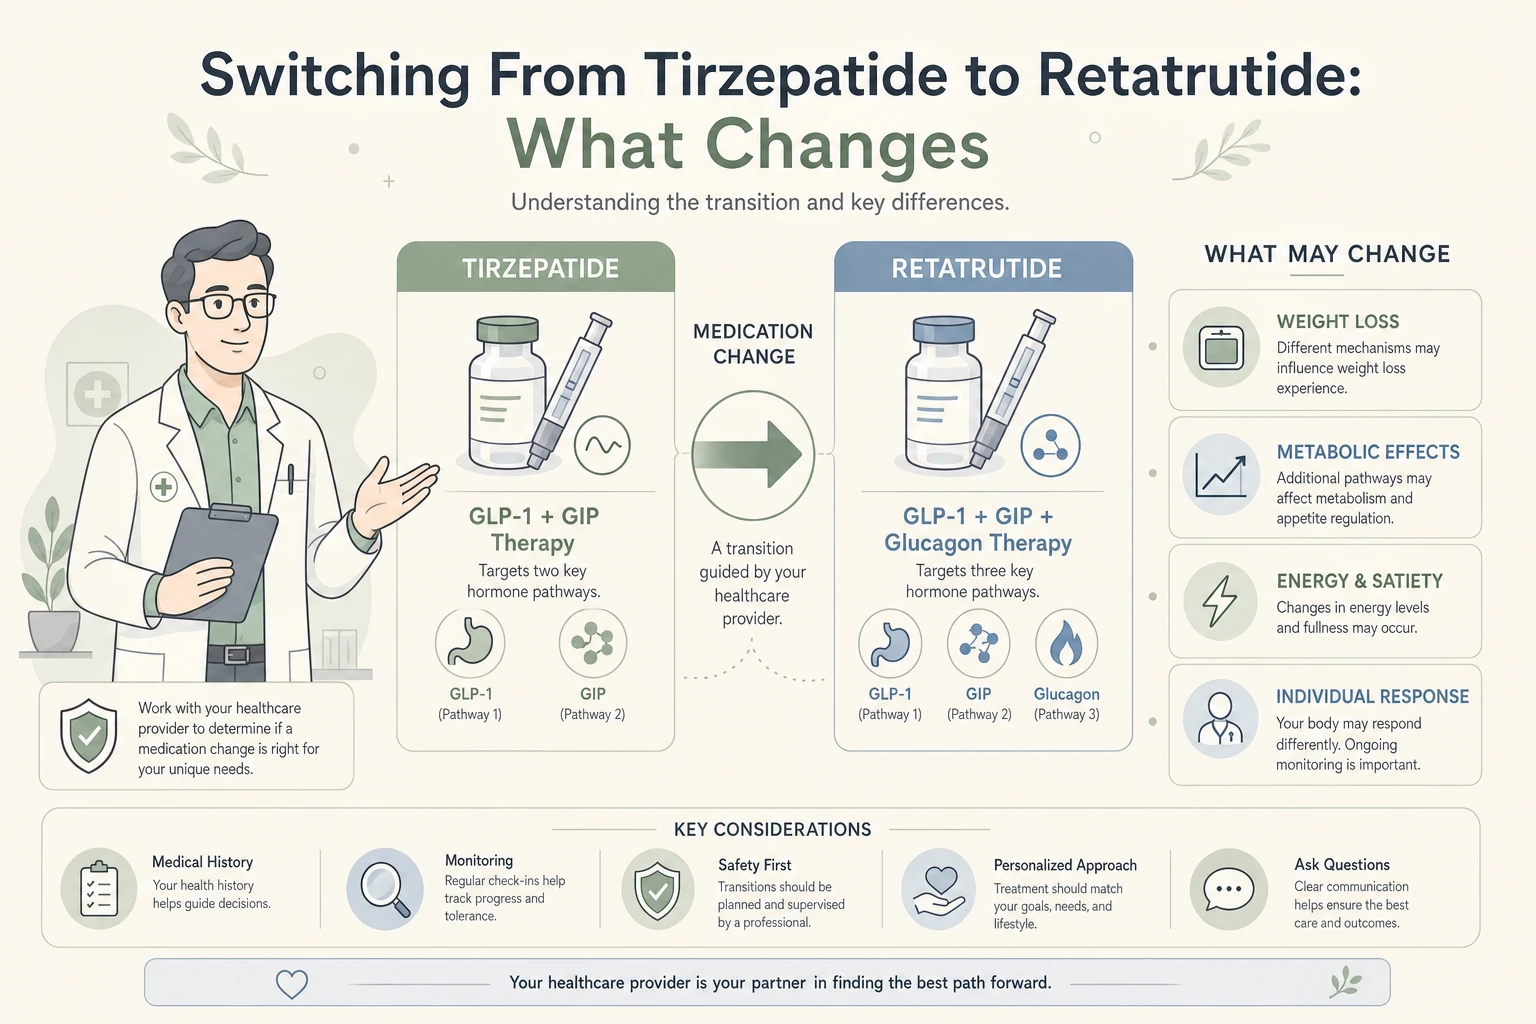
Because retatrutide is a triple agonist acting on GLP-1, GIP, and glucagon receptors, sometimes nicknamed “GLP-3,” its side-effect profile is being watched closely as more patients start it. The pattern so far tracks the same week-by-week logic as the other two medications rather than introducing anything new.

Supporting illustration for GLP-1 Side Effects by Week: What Is Normal, What Passes, What to Report in a modern medical wellness setting

Do Side Effects Change Once You Reach a Maintenance Dose?

Yes, for most patients they drop off sharply once titration ends. The bulk of GLP-1 side effects cluster around the weeks immediately following an increase, so once you stop climbing and settle into a maintenance dose, the body has no new adjustment to make and most gastrointestinal symptoms fade to occasional rather than routine.

What tends to persist longer term is less about the medication’s direct action and more about lifestyle habits that interact with it. Alcohol is a common one patients ask about after they’ve been stable for a few months, since drinking on an empty, slower-emptying stomach can intensify nausea or lower blood sugar in ways that feel different from before starting treatment. Our guide to alcohol and GLP-1 medications covers what actually changes and how to handle it.

Supporting illustration for GLP-1 Side Effects by Week: What Is Normal, What Passes, What to Report in a modern medical wellness setting

What Symptoms Mean You Should Call Your Provider the Same Day?

Severe or persistent abdominal pain, an inability to keep fluids down for more than a day, yellowing of the skin or eyes, or a rapid heartbeat with dizziness are not routine GLP-1 side effects at any week of treatment, whether you are in your first month or your twelfth. Both FDA labels carry warnings for acute pancreatitis and gallbladder disease, and the tirzepatide label separately warns that acute kidney injury has occurred, most often in patients already vomiting or having diarrhea and unable to stay hydrated.

These symptoms warrant a same-day call regardless of how far along you are in titration or how mild your previous side effects have been. A dose increase does not raise the risk of these specific complications in a way that makes them more “expected” later in treatment, and waiting to see if they pass on their own is the wrong instinct for this particular list of symptoms, even for a patient who has otherwise tolerated the medication well for months. If nausea specifically is what’s driving concern, our guide to GLP-1 nausea and stomach side effects covers the full timeline, and constipation is addressed in our fiber and protein guide. Hair thinning, a later and less discussed effect, is covered separately in GLP-1 hair loss.

The most useful question our clinical team asks a patient reporting a symptom isn’t just what it is, it’s when it started relative to the last dose change and whether anything else changed around the same time, like travel, a new medication, or a skipped meal. That single detail usually separates an expected adjustment from something that needs a closer look, and it’s why Body Works reviews titration timing at every follow-up rather than treating each visit as a blank slate.

If a symptom doesn’t fit the expected pattern, or you’re not sure whether what you’re feeling is routine, our physician-supervised teams in Franklin and Nolensville can help you sort it out quickly. Schedule a Free Consultation to get started.

Frequently Asked Questions

Most early side effects ease within a week of starting or increasing a dose, then largely settle until the next scheduled increase. Symptoms that persist unchanged for more than two weeks without a recent dose change are worth discussing with your prescriber.
Trial data suggests the opposite trend for nausea, with tirzepatide running somewhat lower than semaglutide at comparable points in titration, though individual response varies. Neither medication is uniformly easier to tolerate for every patient.
A normal side effect tracks with a recent dose increase and improves within one to two weeks. A red flag, severe abdominal pain, inability to keep fluids down, or yellowing skin or eyes, shows up regardless of timing and needs same-day medical attention rather than a wait-and-see approach.
No. Side-effect monitoring and adjustment are part of a supervised GLP-1 program at Body Works, a cash-pay clinic with payment plans and HSA and FSA eligibility. A free consultation covers program pricing alongside a personalized plan.
Our Franklin office on Murfreesboro Road and our Nolensville office at Burkitt Commons both manage semaglutide, tirzepatide, and retatrutide patients under physician supervision, including side-effect triage by phone between visits. Patients from Brentwood, Spring Hill, Cool Springs, and across Williamson County use whichever office is closer.

Medically reviewed by Dr. Donald Vollmer, MD
Managing Physician, Body Works TN

Browse Our Blog

Ipamorelin vs Sermorelin vs Tesamorelin: Which Growth Hormone Peptide Fits Your Goal

Ipamorelin vs Sermorelin vs Tesamorelin: Which Growth Hormone Peptide Fits Your Goal

October 6, 2026

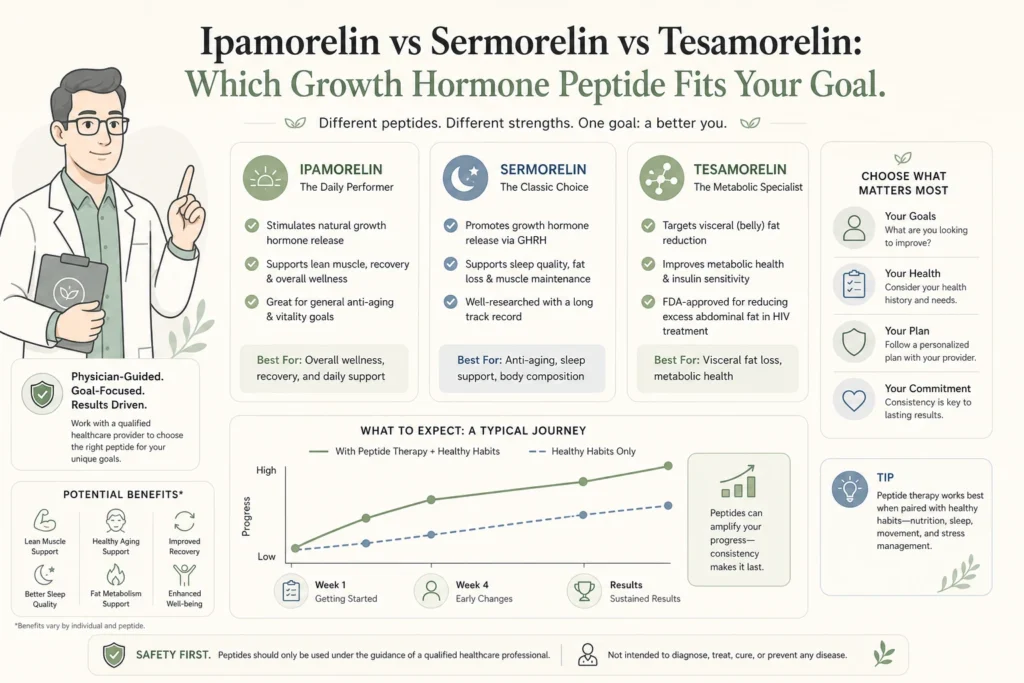
All three of these show up in the same conversation, usually because someone read that they all “boost growth hormone” and assumed that made them interchangeable. They are not. Ipamorelin, sermorelin, and tesamorelin raise growth hormone through three different mechanisms, and the one worth choosing depends entirely on what problem you are trying to solve.

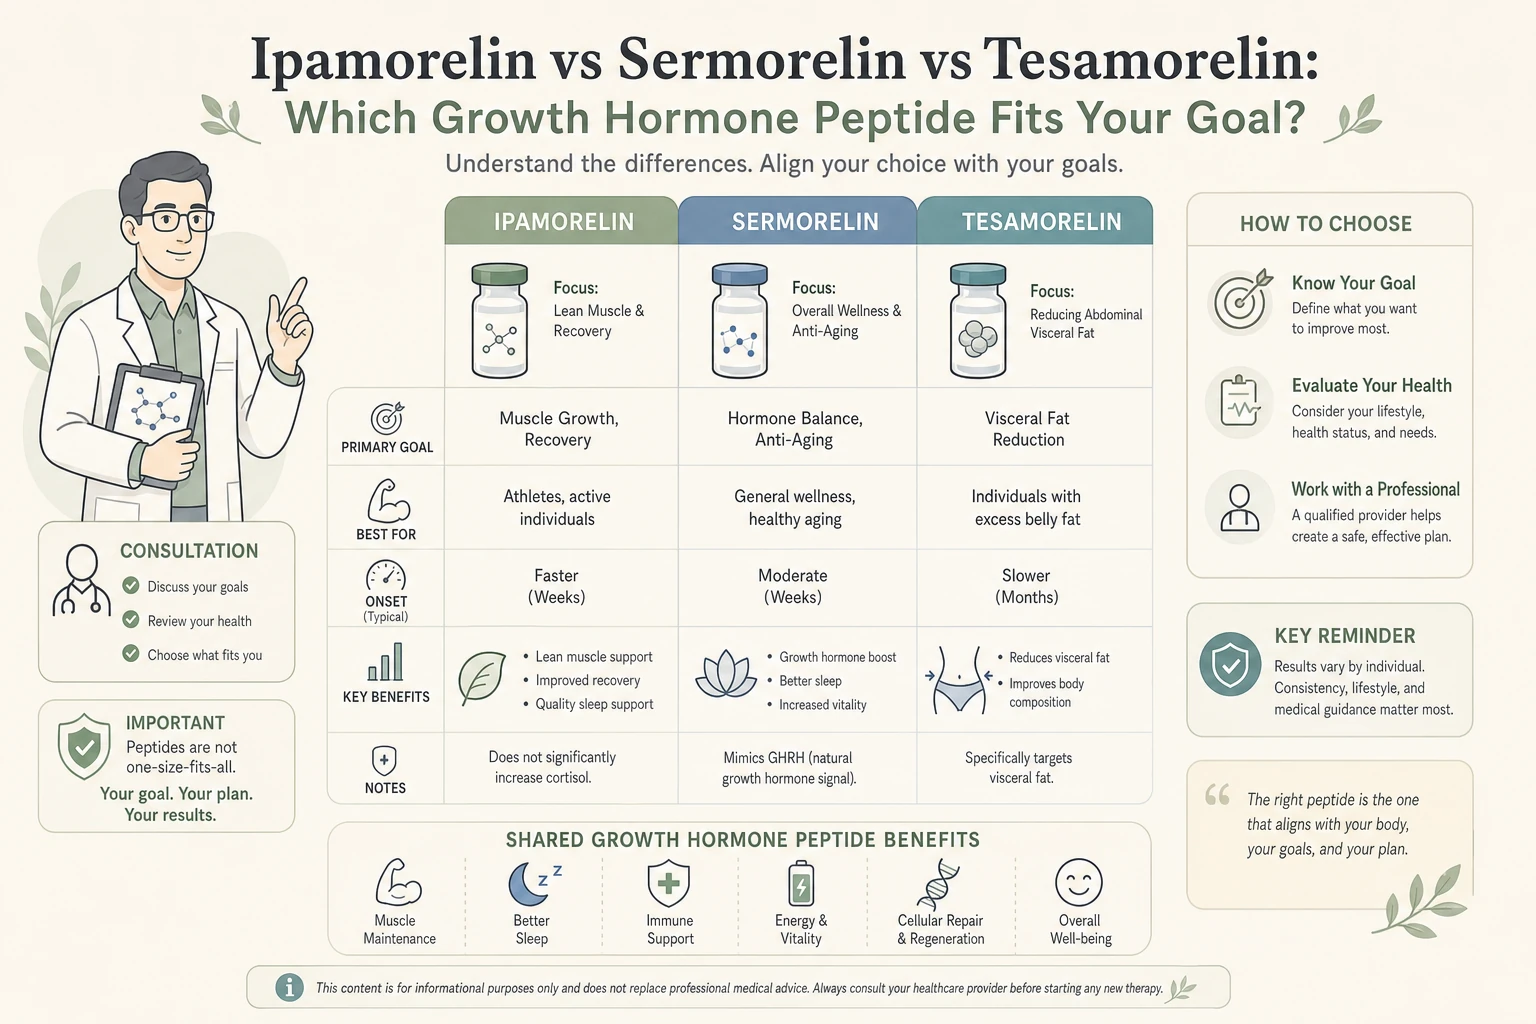
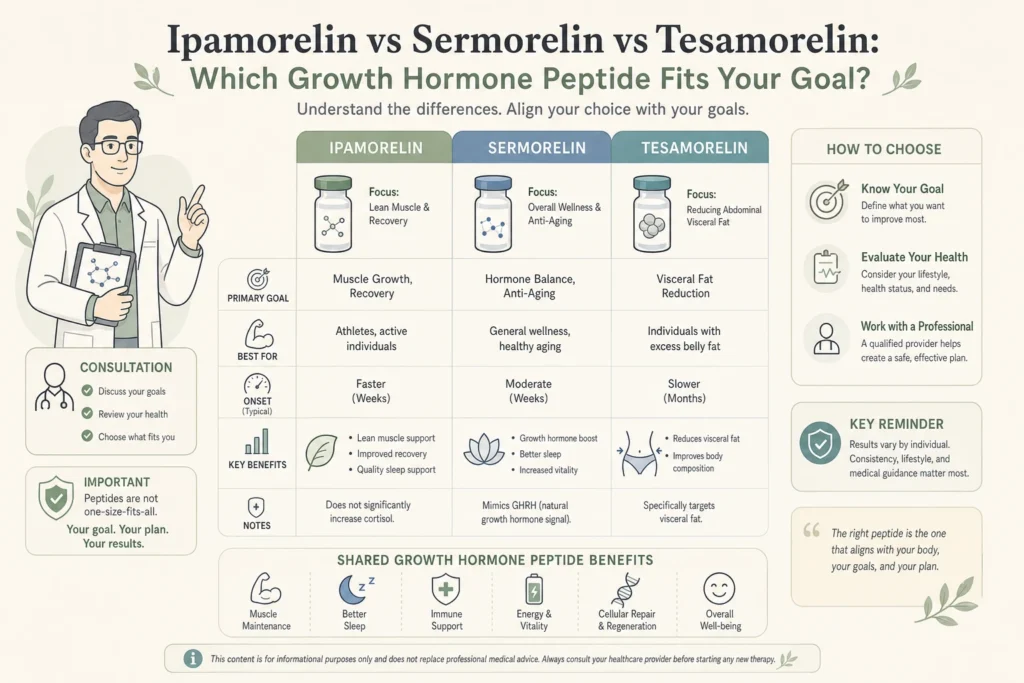
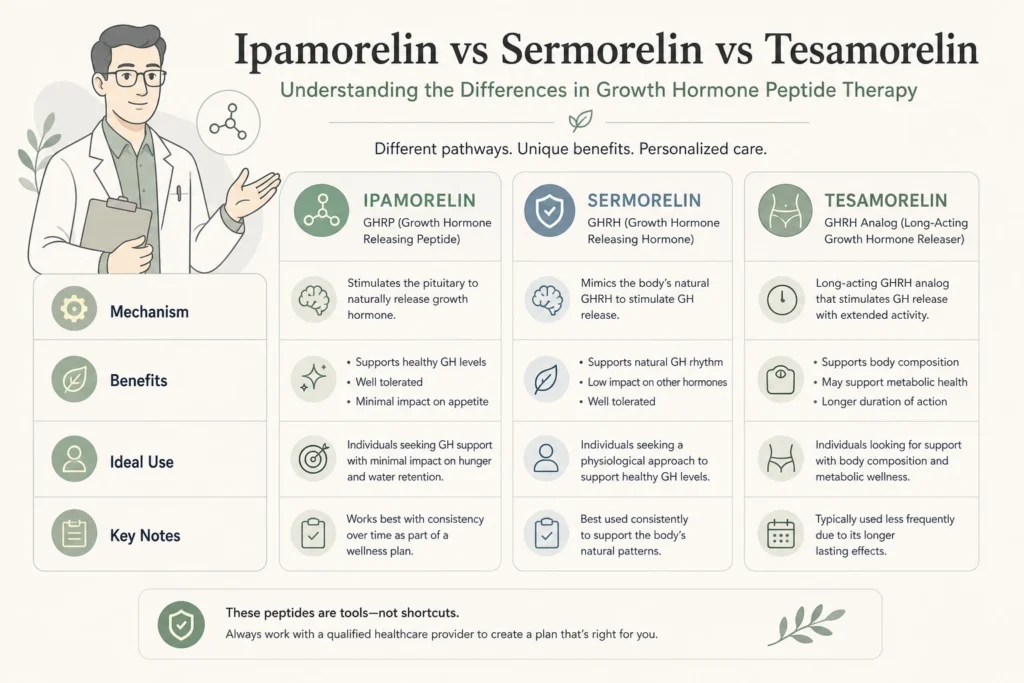
Sermorelin is a growth hormone-releasing hormone analog that stimulates the pituitary’s natural, pulsatile release pattern and has the longest clinical track record of the three. Ipamorelin is a selective ghrelin receptor agonist that triggers growth hormone release without raising cortisol or other hormones, making it the gentlest option on paper. Tesamorelin is a stabilized, more potent GHRH analog with the strongest clinical trial evidence, concentrated specifically in visceral fat reduction. None of the three is simply a stronger or weaker version of the others; they are built differently, on purpose.

Body Works offers physician-supervised protocols for all three at its Nolensville, TN and Franklin, TN offices. Here is what separates them and how a provider matches one to your goal.

Illustration of Ipamorelin vs Sermorelin vs Tesamorelin: Which Growth Hormone Peptide Fits Your Goal in a modern medical wellness setting

What Do Ipamorelin, Sermorelin, and Tesamorelin Have in Common?

All three increase growth hormone output from the pituitary gland, and all three are given as subcutaneous injections rather than pills, because growth hormone-axis peptides do not survive oral digestion intact. Beyond that, the similarities mostly end. Each targets a different receptor system, has a different depth of clinical trial evidence behind it, and is reasonably matched to a different goal, general wellness and sleep quality, a more selective and minimal-side-effect release pattern, or measurable visceral fat reduction.

How Does Sermorelin Work?

Sermorelin is a synthetic 29-amino-acid fragment of growth hormone-releasing hormone that retains the full biological activity of the much larger natural hormone. It binds the GHRH receptor on pituitary cells and stimulates the gland’s own pulsatile release pattern, rather than flooding the body with growth hormone directly, which is part of why it is considered a more physiologic approach than direct growth hormone injections. A published clinical review of sermorelin’s use in diagnosing and treating growth hormone deficiency documented its efficacy and safety profile across a substantial clinical trial history, the deepest evidence base of the three peptides discussed here, even though its original approved use was for growth hormone deficiency rather than general wellness.

How Does Ipamorelin Work, and How Is It Different From Sermorelin?

Ipamorelin works through an entirely different receptor: it is a selective agonist of the ghrelin receptor, which also drives growth hormone release, but through a separate signaling pathway than GHRH does. The original research describing ipamorelin found that it stimulated growth hormone release without meaningfully increasing cortisol, prolactin, or other pituitary hormones, even at doses far above what was needed for its growth hormone effect. That selectivity is the entire reason ipamorelin has the reputation it does: older ghrelin-receptor peptides in the same family raised cortisol and prolactin alongside growth hormone, and ipamorelin was specifically developed to avoid that.

A broader review of growth hormone secretagogues in the management of body composition in hypogonadal men noted that adverse effects with ipamorelin were rare and comparable to sermorelin’s safety record, which is a meaningful finding since it means the selectivity does not come at the cost of a worse safety record.

Supporting illustration for Ipamorelin vs Sermorelin vs Tesamorelin: Which Growth Hormone Peptide Fits Your Goal in a modern medical wellness setting

How Does Tesamorelin Work, and Why Is It Studied for Visceral Fat?

Tesamorelin is a stabilized synthetic GHRH analog, more potent and longer-acting than sermorelin, that binds the same GHRH receptor but produces a stronger and more sustained growth hormone response. It has the most rigorous clinical trial record of the three, built around a specific outcome: visceral fat reduction. A post hoc analysis of a phase 3 placebo-controlled trial found that tesamorelin produced a measurable and consistent reduction in visceral adipose tissue across the study population, and a more recent analysis in patients on modern antiretroviral regimens confirmed tesamorelin maintained both efficacy and a favorable safety profile in that population. The trial evidence behind tesamorelin is specifically about visceral fat, the metabolically active fat around internal organs, not general body composition or growth hormone deficiency the way sermorelin’s evidence is.

FactorSermorelinIpamorelinTesamorelin
Receptor targetGHRH receptorGhrelin receptorGHRH receptor
Best-matched goalGeneral wellness, sleep, natural GH rhythmMinimal side-effect selective GH releaseVisceral fat reduction
PotencyModerateModerateHigher, longer-acting
Effect on other hormonesMinimal at typical useMinimal; does not raise cortisol or prolactinMinimal at typical use
Depth of clinical trial evidenceExtensive, decades of useModerate, strong mechanism dataMost rigorous, phase 3 trial data

Can Ipamorelin, Sermorelin, or Tesamorelin Be Combined?

Ipamorelin is frequently paired with CJC-1295, a longer-acting GHRH analog, rather than with sermorelin or tesamorelin, since combining two peptides that hit the same receptor rarely adds meaningful benefit over using the stronger one alone. The detailed comparison of sermorelin against the CJC-1295 and ipamorelin combination covers that specific pairing decision in more depth than fits here. Tesamorelin, because its evidence is built around a specific outcome, visceral fat, is more commonly used on its own for that goal rather than added into a combination protocol. A provider reviewing your goals and bloodwork is the right way to decide whether a combination makes sense for you, rather than assuming more peptides automatically means a better result.

Supporting illustration for Ipamorelin vs Sermorelin vs Tesamorelin: Which Growth Hormone Peptide Fits Your Goal in a modern medical wellness setting

Which One Should You Choose?

Start with the goal, not the peptide. If general wellness, sleep quality, and a natural growth hormone rhythm are the priority, sermorelin’s long track record makes it the reasonable starting point. If minimizing any effect on cortisol or prolactin matters most, ipamorelin’s selectivity is the differentiator. If the specific concern is visceral fat, the fat that sits around organs and is linked to metabolic risk, tesamorelin has the strongest clinical trial evidence behind that particular outcome. A physician reviewing bloodwork, goals, and health history is the appropriate way to make this decision, not a forum thread comparing anecdotal results.

Supporting illustration for Ipamorelin vs Sermorelin vs Tesamorelin: Which Growth Hormone Peptide Fits Your Goal in a modern medical wellness setting

Growth Hormone Peptides in Nolensville, TN

The question the Nolensville team hears most often is not “which peptide is strongest,” it is “which one actually matches what I’m dealing with.” A patient asking about sleep and general energy gets steered toward a different conversation than one whose bloodwork shows high visceral fat markers, and that goal-first approach is why the team asks about labs and history before naming a peptide at all. Sorting the goal from the peptide first is what keeps the recommendation from defaulting to whichever option is most talked about online that month.

If you want a physician to review your goals and match them to sermorelin, ipamorelin, or tesamorelin, rather than guessing based on what sounds most popular, the Nolensville and Franklin teams can help. Schedule a Free Consultation to get started, or read more about tesamorelin’s specific evidence for visceral fat.

Frequently Asked Questions

Neither is universally better; they work through different receptors and suit different goals. Ipamorelin’s advantage is selectivity, minimal effect on other pituitary hormones, while sermorelin has the longer clinical track record. The right choice depends on what you are trying to achieve.
Cost varies by which peptide, or combination, your provider recommends and the length of the protocol. Body Works does not publish fixed pricing online because every plan is individualized; your consultation includes a specific cost breakdown along with information on payment plans.
Tesamorelin does raise growth hormone and IGF-1 levels generally, since it works through the same GHRH receptor as sermorelin, but its clinical trial evidence specifically documents visceral fat reduction as the primary measured outcome. Broader body composition or wellness effects have less dedicated trial data behind them.
Sermorelin and CJC-1295, both GHRH analogs, are less commonly paired with each other, but ipamorelin is frequently combined with CJC-1295 rather than sermorelin specifically, since the two GHRH analogs largely overlap in mechanism. A provider can explain which combination, if any, fits your specific goal.
Body Works offers physician-supervised sermorelin, ipamorelin, and tesamorelin protocols at its Nolensville and Franklin, TN offices. A consultation includes bloodwork review so the recommendation is based on your goals and health history, not a generic default.
All three have published safety data showing a generally favorable profile when used under physician supervision with appropriate monitoring, though tesamorelin has the most extensive long-term trial data of the three. Ongoing bloodwork is the standard way a provider tracks safety over time.

Medically reviewed by Dr. Donald Vollmer, MD
Managing Physician, Body Works TN

Browse Our Blog

GLP-1 Nausea and Stomach Issues: What Actually Helps

GLP-1 Nausea and Stomach Issues: What Actually Helps

October 2, 2026

The first injection goes fine. The second one too. Then somewhere around the first dose increase, breakfast stops sounding like a good idea and you start wondering whether this is what the next year looks like. In the FDA label for semaglutide, 44% of patients reported nausea. The label does not say when it stops.

GLP-1 nausea is common and, for most people, temporary. It clusters around dose increases and fades as the body adjusts, usually within a few weeks of each step. It happens because these medications slow how fast your stomach empties and change the signals that tell your brain you’re full. Those are the same actions that produce the weight loss, but nausea itself is not proof the medication is working. The dose schedule and what you eat change how it goes, and a short list of symptoms means you call your provider the same day.

Body Works manages semaglutide and tirzepatide patients under physician supervision in Franklin, TN and Nolensville, TN. What follows is the side-effect conversation that belongs before the first injection.

Illustration of GLP-1 Nausea and Stomach Issues: What Actually Helps in a modern medical wellness setting

Why Do GLP-1 Medications Cause Nausea and Stomach Issues?

Because they slow the movement of food out of your stomach and act on the appetite centers in your brain at the same time. Food sits longer and fullness arrives sooner, so a normal meal can feel like too much. The result is the cluster most patients recognize: nausea, a heavy feeling after small meals, burping, reflux, and in some people vomiting or diarrhea.

The numbers are not small. In the FDA prescribing information for semaglutide, nausea was reported by 44% of patients versus 16% on placebo, vomiting by 24% versus 6%, and burping by 7% versus under 1%. Tirzepatide runs lower on nausea at every dose on its label: the FDA label for tirzepatide reports nausea in 25% to 29% of patients across the 5 mg, 10 mg, and 15 mg doses, against 8% on placebo.

GLP-1 nausea is a predictable effect of two things the medication is designed to do, slowing stomach emptying and increasing fullness signals, which is why it sits at the top of both FDA labels’ adverse-reaction tables. The realistic goal is to keep it mild and short.

How Long Does GLP-1 Nausea Last?

For most patients, days to a few weeks after each dose increase, and then it settles. In the SURMOUNT-1 trial of tirzepatide in the New England Journal of Medicine, gastrointestinal events were the most common side effects, mostly mild to moderate, and occurred primarily during the dose escalation period. The same pattern holds for semaglutide.

The clearest picture comes from a pooled analysis of the STEP 1 to 3 trials published in Diabetes, Obesity and Metabolism, covering 2,117 patients on semaglutide 2.4 mg. It found that 99.5% of gastrointestinal events were non-serious, 98.1% were mild to moderate, and they occurred most often during or shortly after dose escalation. Only 4.3% of patients permanently stopped the medication because of stomach symptoms. Put the other way, fewer than 5 in 100 stopped for that reason.

The calendar matters. Nausea that flares in the week after a dose step and eases by the next injection is the expected course. Nausea that persists at a stable dose for several weeks, or worsens, is the signal to slow down or hold the dose.

Nausea Is Not a Sign the Medication Is Working

A common belief is that feeling sick means the dose is “doing something,” and that people who feel fine must be losing less. The evidence says otherwise. In the same pooled STEP analysis, patients who never had a gastrointestinal side effect lost between 9.6% and 17.1% of their body weight, about the same as the 11.4% to 17.7% lost by patients who did. A formal mediation analysis concluded that gastrointestinal side effects contributed little to the weight loss semaglutide produced.

That finding changes the decision you make on a bad week. If nausea drops away at week six and the scale keeps moving, nothing is wrong. If you feel sick and are tempted to push through because you believe it’s the price of results, you’re paying for something that isn’t buying you anything. The weight loss comes from appetite and fullness signaling over months, not from feeling ill. A dose that keeps you comfortable and consistent beats a dose that makes you skip injections.

For the same reason, a lower maintenance dose is a legitimate end point for some patients. The approach to microdosing and maintenance on GLP-1 medications covers how that decision gets made once the initial weight comes off.

Supporting illustration for GLP-1 Nausea and Stomach Issues: What Actually Helps in a modern medical wellness setting

What Can You Do About GLP-1 Nausea Today?

Eat smaller amounts more often and keep drinking. For the first few days after a dose change, keep fat low. A 2025 joint nutrition advisory from four medical societies published in Obesity notes that nausea often occurs in the morning or after long stretches without eating, that skipping meals because of nausea makes it worse, and that vomiting is more likely after large meals. Its advice is a small breakfast followed by small meals every three to four hours, with adequate fluids. Fatty and high-fiber foods are the ones to avoid during the first few days of treatment. Ginger or peppermint tea and acupressure bands are listed as options that can help.

A multidisciplinary expert consensus in the Journal of Clinical Medicine adds the clinical side: how to reach the maintenance dose, what to do when stomach symptoms appear during escalation, and how to minimize nausea, vomiting, diarrhea, and constipation, steps the authors say may keep patients from withdrawing from treatment.

In practice that looks like bland, lower-fat foods on injection day and the day after (toast, rice, eggs, yogurt, lean protein, broth-based soups), with fluids sipped through the day instead of large volumes with meals. Stay upright after eating, since lying down on a full, slow-emptying stomach is the fastest way to turn nausea into reflux. If the first day after each dose is your worst, ask your prescriber about injection timing.

If constipation is the symptom instead, it needs its own plan built around fiber, protein, and fluid. The guide to managing GLP-1 constipation with fiber and protein targets covers that, and the companion article on what to eat on GLP-1 medications covers the food list.

How Does Dose Titration Reduce Stomach Side Effects?

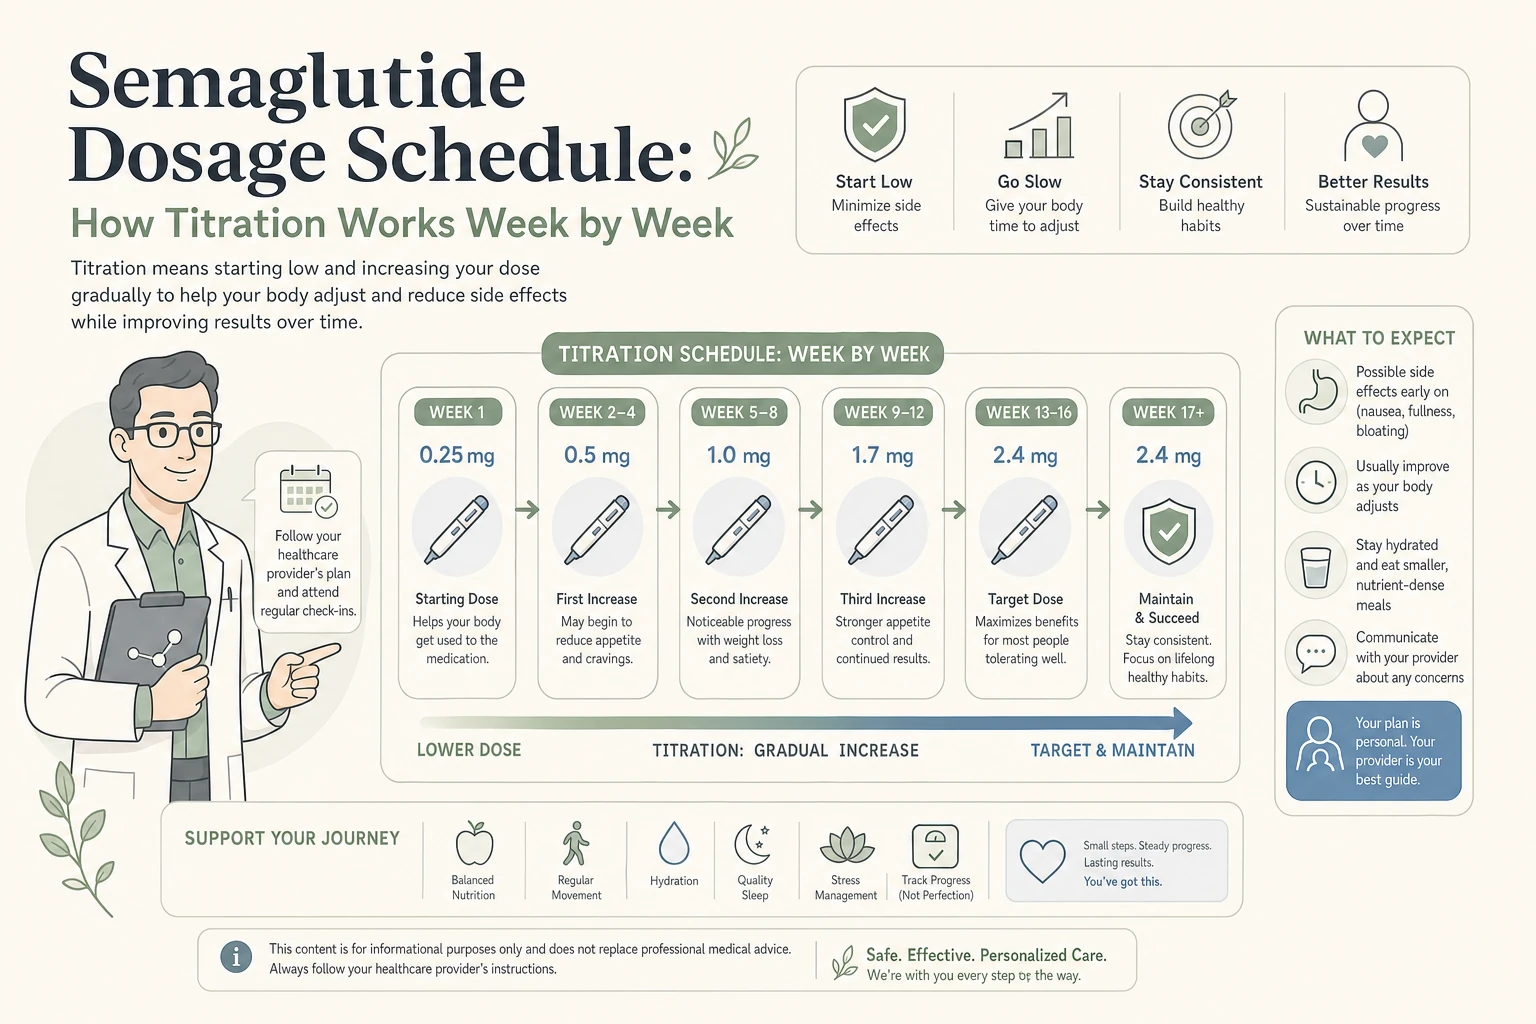
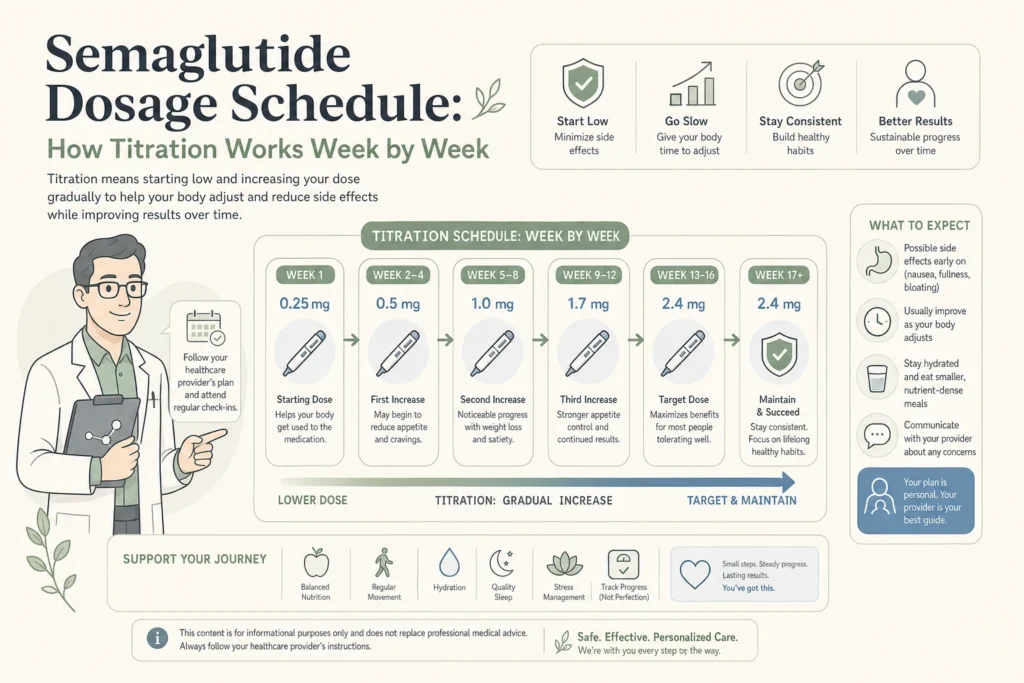
By giving your digestive system weeks to adapt to each level of the medication before the next increase. Semaglutide starts at 0.25 mg weekly for four weeks and steps up through 0.5 mg, 1 mg, and 1.7 mg before reaching the 2.4 mg maintenance dose at week 17, a schedule the label states exists to minimize gastrointestinal adverse reactions. Tirzepatide begins at 2.5 mg and increases in 2.5 mg steps no faster than every four weeks. The tirzepatide label notes that most nausea, vomiting, and diarrhea occurred during dose escalation and decreased over time.

The schedule on the label is a ceiling on speed, not a requirement to climb. A patient who is still queasy at 0.5 mg in week eight does better holding there for another four weeks, the delay the semaglutide label itself suggests, than stepping up on time. The 2025 nutrition advisory notes that trial participants were allowed to stay at a dose for up to eight weeks to let stomach symptoms settle. After a gap, the semaglutide label directs that if more than two consecutive doses are missed, restarting at a lower dose and re-escalating may reduce the stomach symptoms that come with reinitiation.

Titration is the most useful nausea tool the label gives you, and it only works when someone is watching the dose, the symptom, and the calendar together. The tirzepatide dosing guide and the medical weight loss program treat the escalation schedule as a starting point that gets adjusted to the patient.

Side effect (FDA label, versus placebo)Semaglutide 2.4 mgTirzepatide 5 mg to 15 mg
Nausea44% vs 16%25% to 29% vs 8%
Diarrhea30% vs 16%19% to 23% vs 8%
Vomiting24% vs 6%8% to 13% vs 2%
Constipation24% vs 11%11% to 17% vs 5%
Stopped treatment for stomach symptoms4.3% vs 0.7%4.3% at 15 mg vs 0.5%
Supporting illustration for GLP-1 Nausea and Stomach Issues: What Actually Helps in a modern medical wellness setting

Which Stomach Symptoms Mean You Should Call Your Provider?

Ordinary nausea can wait for your next check-in. Pain, dehydration, and vomiting that won’t stop cannot. The MedlinePlus drug guide for semaglutide injection, revised in May 2026, lists nausea, vomiting, diarrhea, stomach pain, constipation, heartburn, and burping as expected side effects to report if they are severe or do not go away. It separates out a shorter list that calls for immediate medical attention:

  • Ongoing pain that begins in the upper left or middle of the stomach and may spread to the back, with or without vomiting, which can signal pancreatitis.
  • Pain in the upper stomach with yellowing of the skin or eyes, fever, or clay-colored stools, which can signal a gallbladder problem.
  • Decreased urination, or swelling of the legs, ankles, or feet.
  • Severe stomach or intestinal problems.

Dehydration is the one that catches people. Both FDA labels warn that acute kidney injury has occurred in patients whose nausea, vomiting, or diarrhea left them dehydrated. If you can’t keep fluids down, or you’re dizzy when you stand, that’s a same-day call, not a wait-and-see. The tirzepatide label also carries postmarketing reports of ileus, a bowel that has stopped moving, so severe abdominal pain with bloating and no bowel movement belongs on the urgent list as well.

Supporting illustration for GLP-1 Nausea and Stomach Issues: What Actually Helps in a modern medical wellness setting

What Side-Effect Support Looks Like in Franklin and Nolensville

In 2025, Body Works guided more than 130 patients through its medical weight loss program at the Nolensville office alone, and the side-effect conversation is built into the first visit. Patients starting semaglutide or tirzepatide leave with written nutrition and symptom guidance. When a patient reports a digestive side effect, the team reviews what they have been eating and drinking and when the symptom began relative to the last dose increase, because those two facts usually point to the fix: a food change, a fluid change, or a slower climb.

If you are considering a GLP-1 medication and want the side effects handled properly, or you’re already on one and feeling worse than you think you should, the Franklin and Nolensville teams can build the plan around you. Schedule a Free Consultation to get started.

Frequently Asked Questions

Usually days to a few weeks after each dose increase, easing before the next step. In the pooled STEP trials, 98% of stomach side effects were mild to moderate and most occurred during or just after escalation. Nausea that persists for weeks at a stable dose is the signal to talk to your prescriber about holding or lowering the dose.
Don’t stop or skip doses on your own. Call your prescriber instead, because holding at the current dose or stepping down is usually the better move and keeps you on schedule. The semaglutide label notes that missing more than two consecutive doses may mean restarting at a lower dose to avoid a return of stomach symptoms.
The FDA labels suggest so: nausea in 25% to 29% of tirzepatide patients versus 44% of semaglutide patients, with vomiting also lower. Those figures come from separate trials with no head-to-head comparison, so treat the gap as a tendency, and remember that both medications are titrated slowly for the same reason.
Side-effect management is included in the program, and pricing depends on the medication and plan you choose. Body Works is a cash-pay clinic with payment plans and HSA and FSA eligibility, and the free consultation is where you get the exact figure along with your titration plan.
The Franklin office on Murfreesboro Road and the Nolensville office at Burkitt Commons both manage semaglutide and tirzepatide patients under physician supervision, including dose adjustments and nutrition support. Patients from Brentwood, Spring Hill, Cool Springs, and across Williamson County use whichever location is closer.

Medically reviewed by Dr. Donald Vollmer, MD
Managing Physician, Body Works TN

Browse Our Blog

Semaglutide in Nolensville, TN: Availability and How to Start

Semaglutide in Nolensville, TN: Availability and How to Start

September 30, 2026

Searching for semaglutide in a town the size of Nolensville turns up a strange gap: national telehealth ads everywhere, but almost nothing about a real clinic nearby that will see you in person, run labs, and adjust your dose as you go. That gap is exactly why patients end up guessing whether a mail-order prescription is even appropriate for them.

Here is the direct answer. Semaglutide is available now for physician-supervised weight loss at the Nolensville, TN office on Burkitt Commons Avenue, with a sister program in Franklin, TN. At Body Works, a physician evaluates you in person before writing a prescription, which matters in a fast-growing suburb where the closest weight-loss specialist used to mean a drive into Nashville. This guide covers how semaglutide works, what local availability actually looks like, and how to start.

Illustration of Semaglutide in Nolensville, TN: Availability and How to Start in a modern medical wellness setting

How Does Semaglutide Work?

Semaglutide is a once-weekly injectable medication that activates the GLP-1 receptor, slowing digestion and reducing appetite while helping regulate blood sugar. It belongs to the same broad hormone-receptor family as newer dual and triple agonist medications, but it was the first to bring double-digit average weight loss into routine clinical use.

In the trial that set that standard, adults with overweight or obesity lost an average of 14.9 percent of body weight over 68 weeks on semaglutide, against 2.4 percent on placebo (STEP 1 trial, New England Journal of Medicine, 2021). That is the number most new patients have already seen online before their first visit.

Because semaglutide targets GLP-1 only, it is a different drug class from dual-receptor medications. If you are weighing the two, our comparison of semaglutide and tirzepatide walks through how the receptor difference shows up in results and side effects.

Is Semaglutide Available in Nolensville, TN?

Yes. Semaglutide is available now at the Nolensville office, and it is prescribed on-site after a physician evaluation rather than mailed out based on an online form. For a town that has grown quickly without a matching increase in specialty medical offices, that means patients no longer have to drive to Franklin, Brentwood, or Nashville just to start a supervised program.

National guidance is consistent on this point: prescription weight-management medications are intended to support diet and activity changes under a clinician’s care, and the decision to start or continue one should be made jointly with that clinician (NIDDK overview of prescription medications for overweight and obesity).

Nolensville’s population more than doubled between the 2010 and 2020 census, from under 6,000 residents to nearly 14,000, and the pace of new subdivisions since then has outrun the number of specialty medical offices in town. The Body Works office on Burkitt Commons Avenue puts a physician-supervised weight-loss program inside Nolensville itself, so patients no longer have to make the drive north to Franklin or into Nashville that a program like this used to require.

Why a Nearby Physician Beats a Mail-Order Prescription

Supervision matters because dose increases and side effects like nausea need a clinician who can actually examine you, not a script that auto-approves a template dose. In a town without many nearby specialty options, a mail-order plan can look like the only choice, but it comes with no one nearby to call if something feels wrong.

Clinical guidance on obesity treatment describes it as an ongoing process, not a one-time prescription: start medication when lifestyle changes alone fall short, then reassess and adjust based on how the patient responds (NIDDK guidance on treating adult overweight and obesity). That kind of adjustment requires an actual relationship with a provider.

In-person care also means your labs and medication history are reviewed before your first dose, and a real clinician nearby if nausea or dehydration becomes more than mild. If that level of oversight matters to you, the next step is to Schedule a Free Consultation.

Supporting illustration for Semaglutide in Nolensville, TN: Availability and How to Start in a modern medical wellness setting

Your First Semaglutide Appointment at the Nolensville Office

You start with a consultation and baseline bloodwork at the Nolensville office, then a physician reviews the results before writing a prescription and setting your starting dose. From there, the dose increases gradually on a titration schedule instead of jumping straight to a full therapeutic level.

Semaglutide is a once-weekly subcutaneous injection, and your provider demonstrates the technique and injection sites in the office before you take a dose home (MedlinePlus patient information on semaglutide injection). Most patients begin at the lowest dose and step up slowly to limit nausea.

Staying on treatment is part of what makes it work. In the STEP 4 trial, patients who continued semaglutide after the first 20 weeks lost a further 7.9 percent of their body weight by week 68, while those switched to placebo regained 6.9 percent (STEP 4 trial, JAMA, 2021). Regular follow-up visits are what keep that progress from reversing.

Nutrition guidance is built into the plan from the start. Eating enough protein and smaller, slower meals helps control nausea and preserve muscle while losing weight, which is why semaglutide at Body Works pairs with a practical guide to eating on GLP-1 therapy.

Starting semaglutide at the Nolensville office follows the same sequence for every new patient:

  1. Schedule a free consultation and complete a health history intake.
  2. Baseline bloodwork drawn at the Nolensville office, reviewed by a physician.
  3. Physician confirms candidacy and writes a starting-dose prescription.
  4. In-office injection walkthrough before you take the first dose home.
  5. Follow-up visits on a titration schedule as the dose increases.
Supporting illustration for Semaglutide in Nolensville, TN: Availability and How to Start in a modern medical wellness setting

Are You a Good Candidate for Semaglutide?

Good candidates are generally adults with a higher body mass index, or a somewhat lower BMI combined with a weight-related condition such as high blood pressure, high cholesterol, or type 2 diabetes. A consultation at the Nolensville office confirms whether semaglutide fits your health picture.

Semaglutide has specifically been studied in adults with type 2 diabetes, where patients on the medication lost significantly more weight than those on placebo while also improving blood sugar management (STEP 2 trial, The Lancet, 2021). For patients managing both weight and blood sugar, that makes it a frequent starting point.

Life stage and hormones factor into candidacy too. If hormone therapy is also on your radar, our overview of GLP-1 medications and hormone therapy for women explains how the two are typically coordinated. Pregnancy and a personal or family history of certain thyroid tumors rule the medication out, and the evaluation screens for both before anything is prescribed.

Supporting illustration for Semaglutide in Nolensville, TN: Availability and How to Start in a modern medical wellness setting

Starting Semaglutide in Nolensville and Franklin

Getting started begins with a conversation, not a commitment. At Body Works, semaglutide is one part of a broader medical weight loss program, and the Nolensville medical weight loss program pairs the medication with physician oversight, lab monitoring, and nutrition guidance from day one. Patients in Nolensville and Franklin get the same supervised process at either office.

If cost is what is holding you back, the consultation is where payment plans and HSA or FSA eligibility are reviewed, with no pressure to commit that day. The next step is simple: Schedule a Free Consultation, and the Nolensville team will help you figure out whether semaglutide is the right fit.

Frequently Asked Questions

Yes. Semaglutide is prescribed and monitored on-site at the Nolensville office on Burkitt Commons Avenue, so residents no longer need to drive to Franklin or Nashville for a physician-supervised program with regular follow-up visits.
Cost depends on your dose and treatment plan, so the most accurate answer comes from a visit rather than a price list. During your free consultation, the Nolensville team reviews payment plans and whether an HSA or FSA applies, with no obligation to start that day.
Yes. Baseline bloodwork and a review of your medical history happen before any prescription is written, so your physician can confirm semaglutide is appropriate and safe for you.
Semaglutide activates only the GLP-1 receptor, while tirzepatide activates both GLP-1 and GIP receptors. Head-to-head research has shown somewhat greater average weight loss with tirzepatide, but the right choice depends on health history and tolerance, which a consultation sorts out.
Yes. The Nolensville office on Burkitt Commons Avenue offers semaglutide as part of a full physician-supervised program, so patients do not need to travel outside town for consultations, bloodwork, or follow-up visits.

Medically reviewed by Dr. Donald Vollmer, MD
Managing Physician, Body Works TN

Browse Our Blog

Semaglutide in Franklin, TN: Availability and How to Start

Semaglutide in Franklin, TN: Availability and How to Start

September 28, 2026

If you have been researching semaglutide for weight loss, you have probably hit the same wall everyone else does: a telehealth app that ships a vial with almost no physician contact, or a local clinic page that never actually says whether the medication is in stock. Neither one tells you what you actually need to know, which is who is supervising your dose and what happens when a side effect shows up.
Here is the direct answer. Semaglutide is available now for physician-supervised weight loss in Franklin, TN, with a sister program in Nolensville, TN. At Body Works, semaglutide is prescribed after an in-person evaluation at the Murfreesboro Road office, not auto-approved by a questionnaire. If you have been searching for semaglutide in Franklin with a real doctor behind it, this guide covers how the medication works, how local availability holds up, and how to start.

Illustration of Semaglutide in Franklin, TN: Availability and How to Start in a modern medical wellness setting

What Is Semaglutide and How Does It Work?

Semaglutide is a once-weekly injectable medication that activates the GLP-1 receptor, a hormone pathway that slows digestion, reduces appetite, and helps the body manage blood sugar. It is the same receptor class as several other weight-loss medications, but semaglutide was the first to bring 15 percent or greater average weight loss into mainstream use.

In the trial that established that benchmark, adults with overweight or obesity who took semaglutide lost an average of 14.9 percent of their body weight over 68 weeks, compared with 2.4 percent on placebo (STEP 1 trial, New England Journal of Medicine, 2021). That result is why semaglutide is usually the first medication patients ask about by name.

Semaglutide is GLP-1 only, which distinguishes it from dual and triple agonists that also target GIP or glucagon receptors. If you are comparing options, our comparison of semaglutide and tirzepatide breaks down which receptor profile tends to fit which patient.

Is Semaglutide Available in Franklin, TN?

Yes. Semaglutide is available now at the Franklin office on Murfreesboro Road, and patients commuting in from Cool Springs, Brentwood, and Spring Hill start the program here rather than waiting on a mail-order pharmacy to confirm a shipment. The medication is dispensed on-site after a physician reviews your history, not shipped sight unseen.

Federal guidance is direct about this: prescription weight-management medications are meant to be used alongside diet and physical activity changes under a health care professional’s supervision, and choosing to start or continue one is a decision made with a clinician, not an app (NIDDK overview of prescription medications for overweight and obesity).

The Franklin office sits off Murfreesboro Road near the Cool Springs corridor, a stretch built around commuter traffic rather than walk-in retail. That shapes the schedule the team runs: the office opens at 7:00am on Wednesdays and Fridays and at 9:00am on Mondays, Tuesdays and Thursdays, with lunchtime slots on most days, because most Franklin patients are fitting a consultation or a follow-up around a workday.

Why Franklin Patients Choose Physician Supervision Over a Mail-Order Kit

Supervision matters because semaglutide’s side effects, mostly nausea and slowed digestion, are dose-dependent, and someone has to decide when to hold a dose steady versus move up. A questionnaire-based telehealth service rarely adjusts a titration plan in real time; a physician who has examined you can.

Clinical guidance on obesity treatment describes an ongoing process: start medication when lifestyle changes alone are not enough, then reassess whether it is working and adjust the plan (NIDDK guidance on treating adult overweight and obesity). That reassessment is the part a subscription box cannot replicate.

In-person care also means your labs and medication list are reviewed before the first injection, and a real clinician is reachable if nausea or dehydration becomes more than a minor annoyance. If you are ready for that level of oversight, the next step is to Schedule a Free Consultation.

Supporting illustration for Semaglutide in Franklin, TN: Availability and How to Start in a modern medical wellness setting

What Happens at Your First Semaglutide Visit in Franklin?

You start with a consultation and baseline bloodwork at the Franklin office, then a physician reviews your results before writing a prescription and setting a starting dose. The plan is built around gradual titration, so the dose rises over several weeks rather than jumping straight to a therapeutic level.

The medication is a once-weekly subcutaneous injection, and your provider walks through the technique and injection sites directly before you take a dose home (MedlinePlus patient information on semaglutide injection). Most patients start at the lowest dose and step up on a schedule that limits nausea.

Staying on the medication is part of the plan working. In the STEP 4 trial, patients who continued semaglutide after the first 20 weeks lost a further 7.9 percent of their body weight by week 68, while those switched to placebo regained 6.9 percent (STEP 4 trial, JAMA, 2021). Follow-up visits are what keep a plan on track instead of drifting.

Nutrition support runs alongside the medication from day one. Prioritizing protein at each meal and eating slower, smaller portions helps manage nausea and protects muscle mass, which is why the program pairs semaglutide with a practical guide to eating on GLP-1 therapy.

FactorSemaglutideTirzepatide
Receptor targetGLP-1 onlyGLP-1 and GIP (dual)
Dosing scheduleOnce weekly injectionOnce weekly injection
Average weight loss in trials14.9% over 68 weeks (STEP 1)Higher average in head-to-head data
Available at Body Works FranklinYesYes
Supporting illustration for Semaglutide in Franklin, TN: Availability and How to Start in a modern medical wellness setting

Who Qualifies for Semaglutide?

Good candidates are generally adults with a higher body mass index, or a somewhat lower BMI plus a weight-related condition such as high blood pressure, high cholesterol, or type 2 diabetes. A consultation at the Franklin office confirms whether semaglutide fits your health history and whether anything rules it out.

Semaglutide has also been studied specifically in adults with type 2 diabetes, where participants on the medication lost significantly more weight than those on placebo while also improving blood sugar control (STEP 2 trial, The Lancet, 2021). That makes it a common starting point for patients managing both conditions at once.

Candidacy also depends on hormones and life stage. If you are also considering hormone therapy, our overview of GLP-1 medications and hormone therapy for women covers how the two interact. Pregnancy and a personal or family history of certain thyroid tumors are reasons to avoid semaglutide, and the evaluation screens for both.

Supporting illustration for Semaglutide in Franklin, TN: Availability and How to Start in a modern medical wellness setting

Starting Semaglutide in Franklin and Nolensville

Getting started is a conversation, not a commitment. At Body Works, semaglutide is one part of the broader medical weight loss program, and the Franklin medical weight loss program pairs the medication with physician oversight, lab monitoring, and nutrition guidance built in from the start. Patients in Franklin and Nolensville get the same supervised process at both offices.

If cost is the hesitation, the consultation is where payment plans and HSA or FSA eligibility get sorted out, with no pressure to start that day. The next step is simple: Schedule a Free Consultation, and the Franklin team will help you decide whether semaglutide is the right fit.

Frequently Asked Questions

Yes. Semaglutide is prescribed and monitored on-site at the Franklin office on Murfreesboro Road, so patients from Franklin, Cool Springs, Brentwood, and Spring Hill can start locally with a physician evaluation and ongoing follow-up visits.
Cost depends on your dose and treatment plan, so the clearest answer comes from a visit rather than a price list. During your free consultation, the Franklin team reviews payment plans and whether an HSA or FSA applies, with no obligation to start that day.
Yes. Baseline bloodwork and a review of your medical history happen before any prescription is written, so your physician can confirm semaglutide is appropriate and safe for you specifically.
Semaglutide activates only the GLP-1 receptor, while tirzepatide activates both GLP-1 and GIP receptors. Head-to-head research has shown somewhat greater average weight loss with tirzepatide, but the right choice depends on your health history and how you tolerate each medication, which a consultation sorts out.
Many Franklin patients notice reduced appetite within the first few weeks, with meaningful weight loss building gradually as the dose increases over the following months. Consistent weekly injections and follow-up visits produce the steadiest results.

Medically reviewed by Dr. Donald Vollmer, MD
Managing Physician, Body Works TN

Browse Our Blog

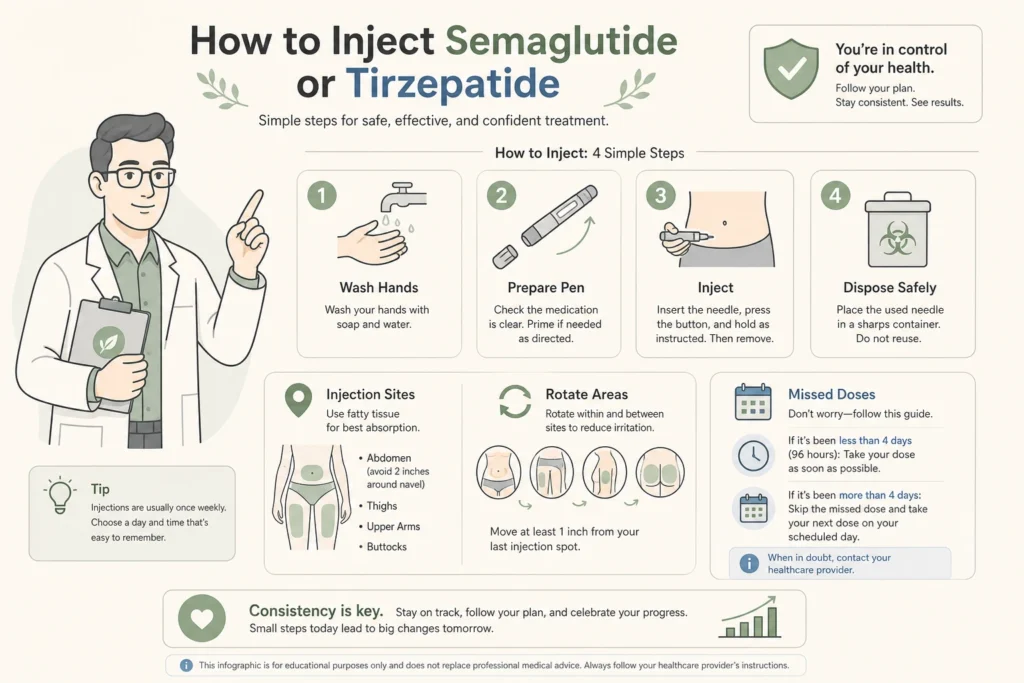
How to Inject Semaglutide and Tirzepatide: Sites, Rotation, and Missed Doses

How to Inject Semaglutide and Tirzepatide: Sites, Rotation, and Missed Doses

September 24, 2026

The needle is the easy part. Most people who quit a GLP-1 medication early do not quit because of the injection itself, they quit because of a bruised, lumpy patch of skin from using the same spot every week, or because a missed dose turned into a guessing game about what to do next.

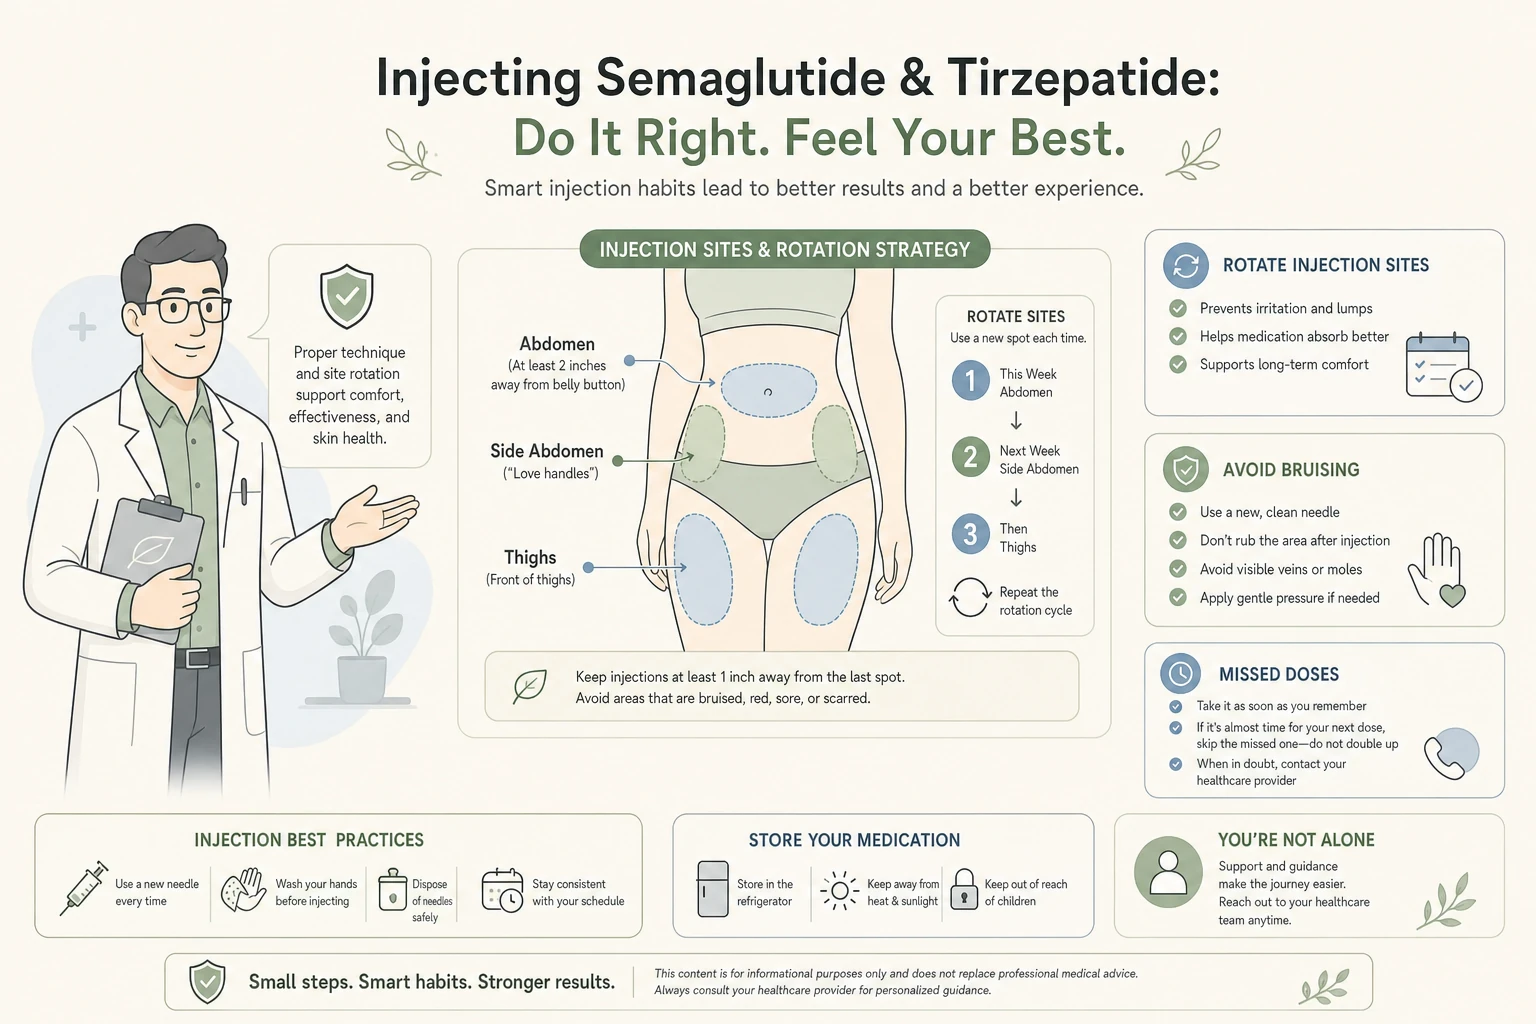
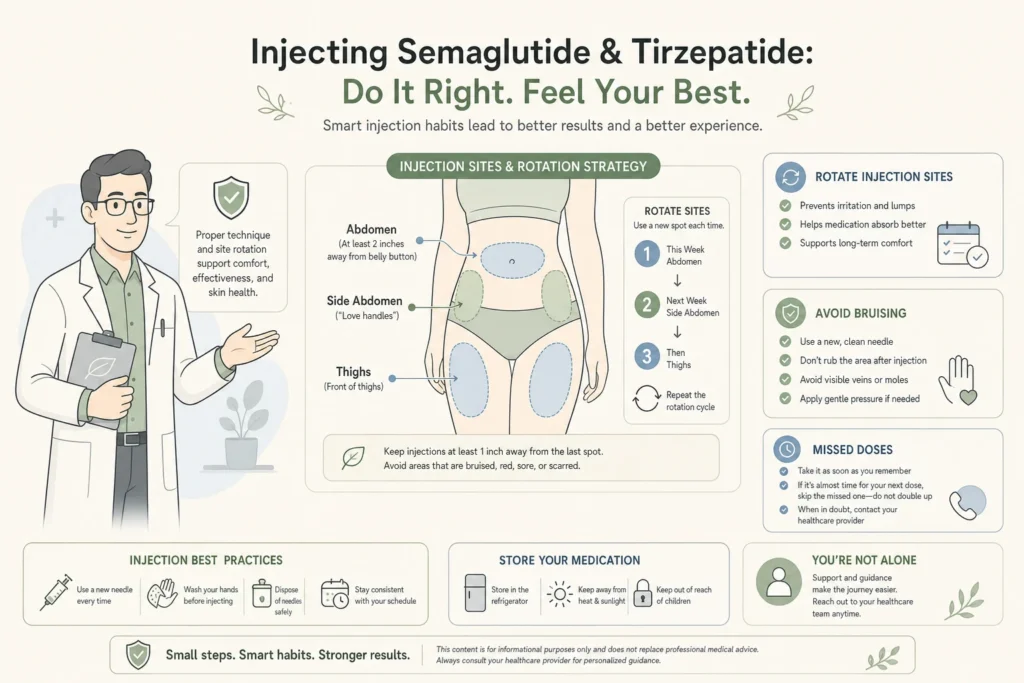
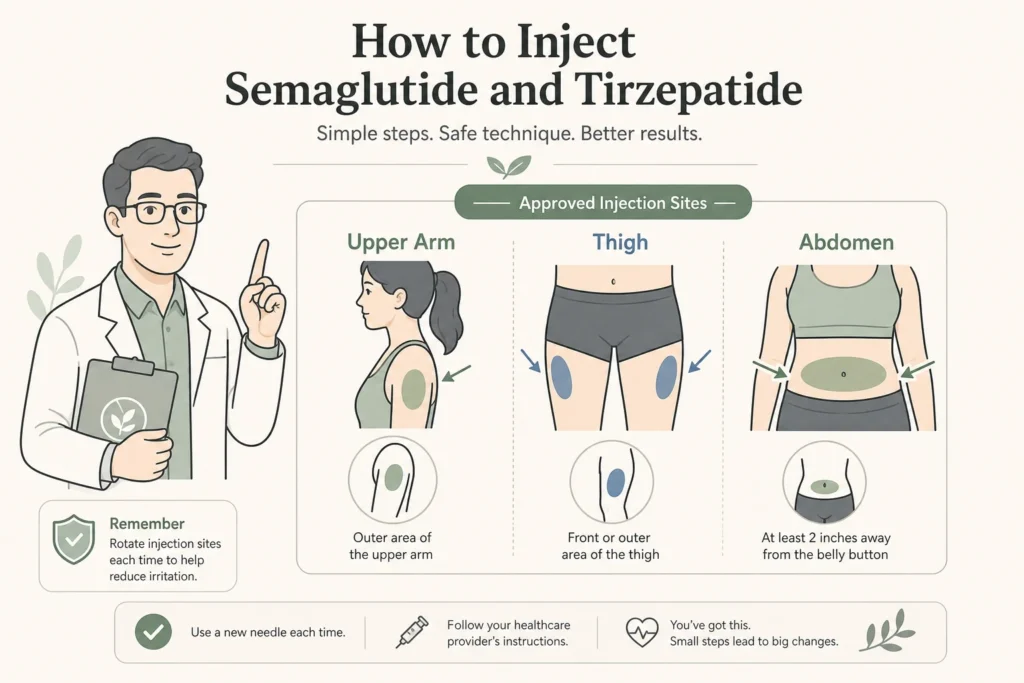
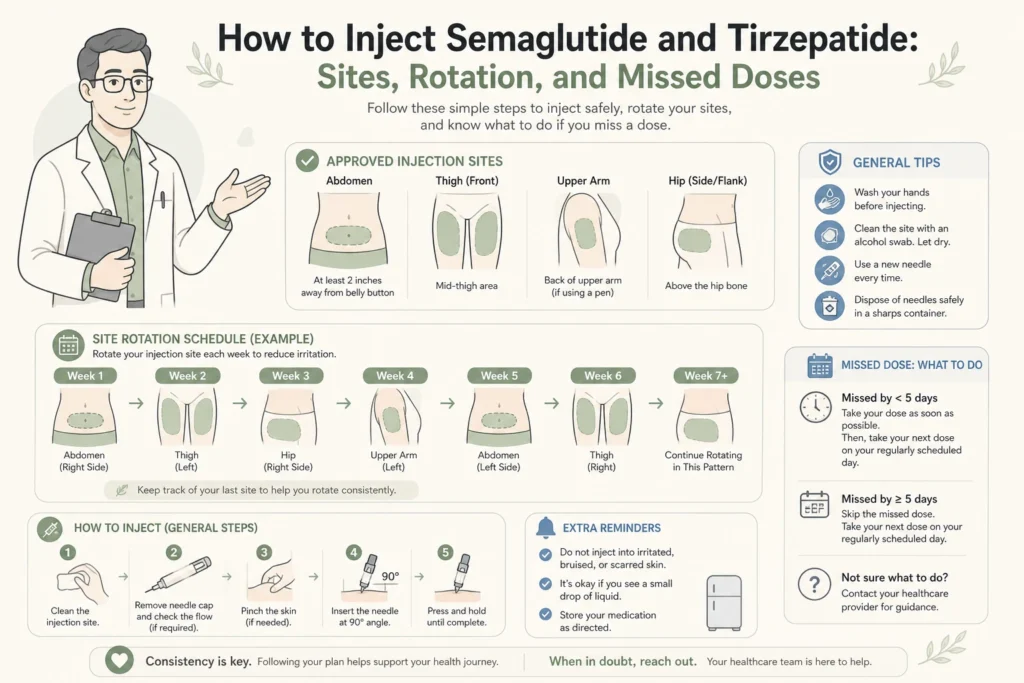
Semaglutide and tirzepatide are both injected subcutaneously, meaning into the fatty layer under the skin, once a week, in the abdomen, thigh, or upper arm, with the injection site rotated every time. Getting that rotation pattern right, and knowing the actual rule for a missed dose instead of guessing, prevents most of the avoidable problems patients run into. Body Works providers in Nolensville, TN and Franklin, TN walk every new patient through this at their first injection before they ever do one alone.

Illustration of How to Inject Semaglutide and Tirzepatide: Sites, Rotation, and Missed Doses in a modern medical wellness setting

Where Do You Inject Semaglutide or Tirzepatide?

Both medications use the same three approved sites: the abdomen, the front of the thigh, and the back of the upper arm. According to the semaglutide injection instructions published by MedlinePlus, injections should stay at least two inches away from the belly button when using the abdomen, and the same spacing rule applies to tirzepatide per its own MedlinePlus drug entry for tirzepatide injection.

No single site is better than the others for absorption. The right choice is whichever area you can comfortably reach and pinch a fold of skin from every week, since consistency in technique matters more than which of the three sites you use on any given day. Most patients settle into a pattern within the first few weeks, rotating between the abdomen and thigh and saving the upper arm for weeks when a partner or family member is available to help.

Why Does Site Rotation Matter So Much?

Injecting the exact same spot week after week causes tissue changes that can stop the medication from absorbing properly, which is the opposite of what a titration schedule is trying to achieve. A Cleveland Clinic guide to subcutaneous injection technique notes that repeated injections in one location cause the tissue to change over time, reducing absorption and increasing bruising and discomfort, and recommends spacing each new injection at least an inch and a half from the last.

A simple rotation habit fixes this: pick a different one of the three approved areas each week, or move roughly a hand’s width across the same area, and keep a mental note of your last injection point. Patients who skip rotation are also the ones most likely to develop the hard lumps that make the next several injections more painful than they need to be.

Site Rotation at a Glance

SitePlacement ruleRotation tip
AbdomenAt least 2 inches from the belly buttonAlternate left and right sides week to week
ThighFront of the thigh, mid-way between hip and kneeAlternate left and right legs
Upper armBack of the upper arm, where a caregiver or partner can help if neededHarder to self-inject, so it works best as an occasional rotation option rather than a weekly default
Supporting illustration for How to Inject Semaglutide and Tirzepatide: Sites, Rotation, and Missed Doses in a modern medical wellness setting

What Is the Correct Injection Technique?

Clean the site, pinch a fold of skin between your thumb and forefinger, and insert the full needle at a 90-degree angle in one steady motion. That’s the same technique the Cleveland Clinic’s guide to giving a subcutaneous injection describes, and it matches the manufacturer instructions printed with these pens. Hold the fold throughout the injection, depress the plunger slowly and fully, and withdraw the needle straight out rather than at an angle, which reduces bruising and leakage at the site.

Both semaglutide and tirzepatide come in prefilled pens designed for self-injection, and the button-style mechanism does most of the depth and angle work automatically once it’s pressed against pinched skin. Checking that the solution is clear and free of particles before every injection, and confirming the pen hasn’t expired, takes less time than the injection itself and prevents a wasted dose. The FDA-approved prescribing information for semaglutide also specifies that pens should be stored refrigerated until first use, then can be kept at room temperature for a limited window once in use, which matters if you travel or keep a pen in a bag between doses.

New patients sometimes worry about hitting a vein or injecting too deep. The subcutaneous layer these medications target sits just under the skin and above the muscle, which is why the pinch-and-hold step matters: it lifts that fatty layer away from deeper tissue before the needle goes in. Watching a nurse demonstrate the first injection in person resolves most of this hesitation faster than any written instructions can.

Supporting illustration for How to Inject Semaglutide and Tirzepatide: Sites, Rotation, and Missed Doses in a modern medical wellness setting

What Should You Actually Do About a Missed Dose?

The rule differs slightly by medication, and guessing wrong in either direction causes real problems. For tirzepatide, MedlinePlus advises taking a missed dose as soon as you remember it if fewer than four days have passed since the scheduled day. Beyond four days, skip it entirely and resume your normal weekly schedule rather than doubling up. Semaglutide follows a similar late-dose window under medical guidance, though the exact cutoff should always be confirmed with your prescriber since it can shift based on where you are in titration.

Never inject two doses within a few days of each other to “catch up.” That raises side-effect risk without adding any benefit, since these medications are designed around steady, once-weekly exposure, not accumulated dosing. If you’re unsure whether enough time has passed to take a late dose safely, call your provider rather than guess, especially during the early weeks of the tirzepatide titration schedule when the body is still adjusting to each new step.

Supporting illustration for How to Inject Semaglutide and Tirzepatide: Sites, Rotation, and Missed Doses in a modern medical wellness setting

When Should an Injection Site Reaction Concern You?

Mild redness, a small bump, or brief tenderness at the injection site is common and usually resolves within a day. What’s not routine is a site that stays hard, warm, or increasingly painful for more than a few days, or spreading redness, which can signal a skin infection rather than a normal injection reaction. Those symptoms, along with the broader picture of what counts as an expected side effect versus one that needs same-day attention, are covered in our guide to GLP-1 side effects by week.

The injection questions our nursing staff hears most often aren’t about the needle itself. They’re about rotation and missed doses, the two details a patient handout easily buries in fine print but that determine whether the next twelve weeks of treatment go smoothly. Body Works reviews injection technique at every follow-up visit, not just the first one, because habits drift over months of self-injecting.

Whether you’re about to give yourself a first injection or you’ve been on either medication for months and want your technique checked, our physician-supervised teams in Franklin and Nolensville can walk through it with you. Schedule a Free Consultation to get started.

Frequently Asked Questions

It’s best not to. Repeated use of the same spot can change the underlying tissue and reduce how well the medication absorbs. Rotate to a different approved site, or a different area within the same site, every week.
For tirzepatide, waiting beyond four days past the scheduled day means skipping that dose entirely and resuming the normal weekly schedule rather than injecting late. Taking two doses close together to compensate increases side-effect risk without added benefit.
Occasional mild bruising is common, especially early on, and usually fades within a few days. Frequent or worsening bruising at the same spot is often a rotation problem, not a medication problem, and switching sites more deliberately typically resolves it.
No. Injection training is included as part of a supervised GLP-1 program at Body Works, a cash-pay clinic with payment plans and HSA and FSA eligibility. A free consultation covers technique, scheduling, and program pricing together.
Our Nolensville office at Burkitt Commons and our Franklin office on Murfreesboro Road both walk new patients through their first injection in person, then check technique again at follow-up visits. Patients from Brentwood, Spring Hill, Cool Springs, and across Williamson County use whichever office is closer.

Medically reviewed by Dr. Donald Vollmer, MD
Managing Physician, Body Works TN

Browse Our Blog

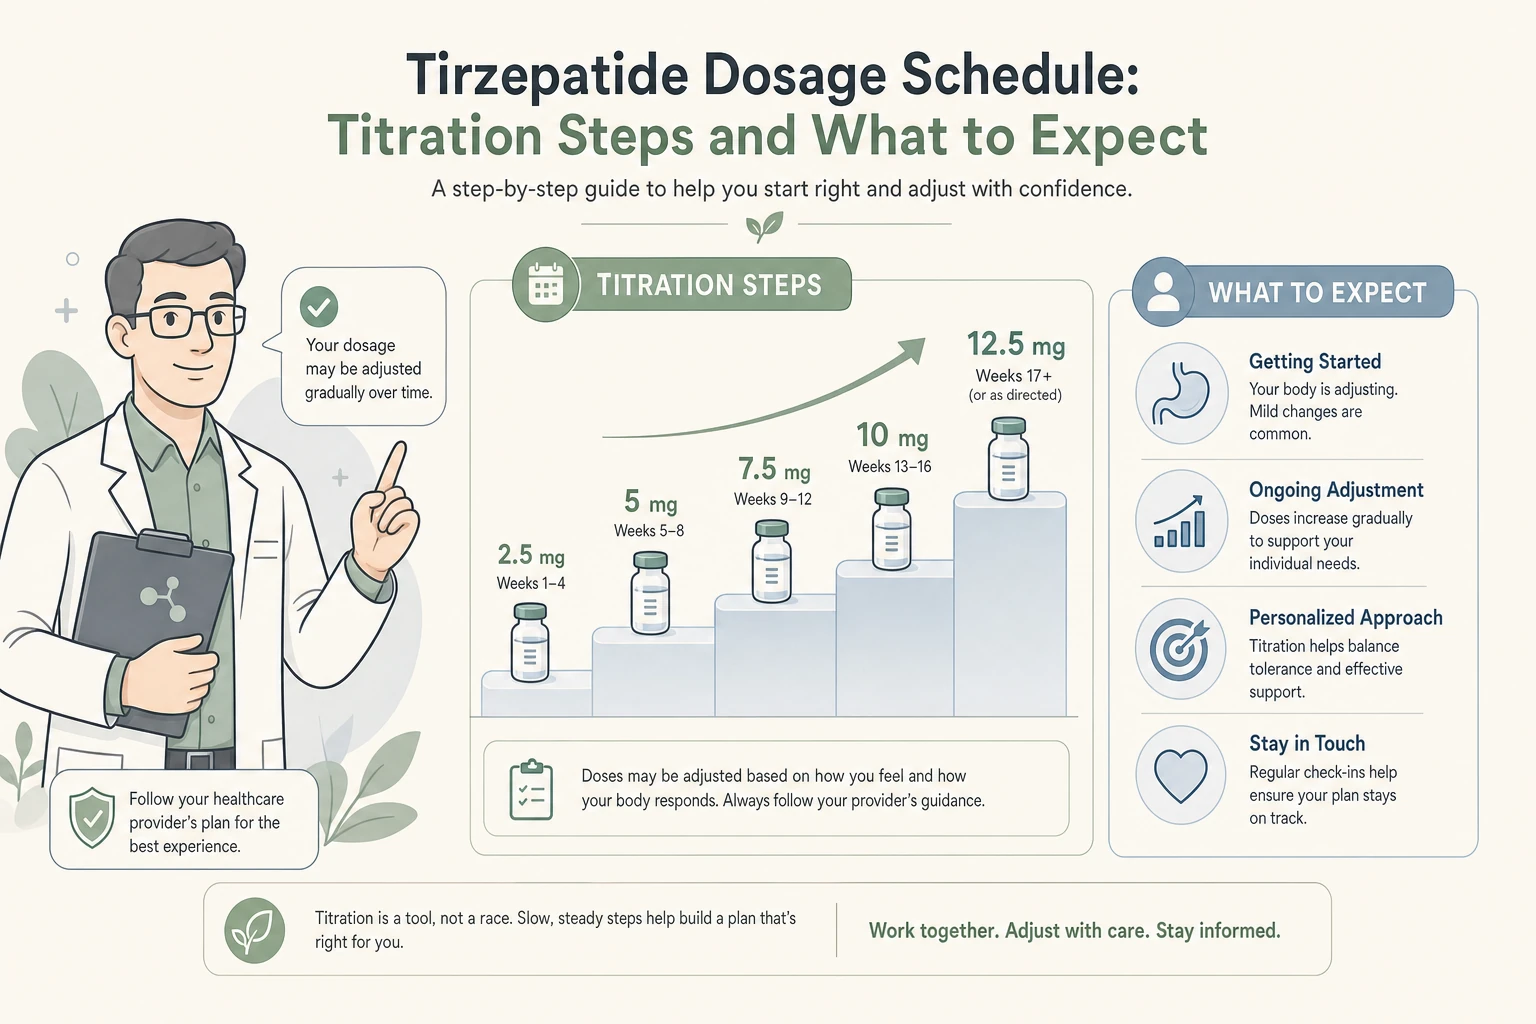
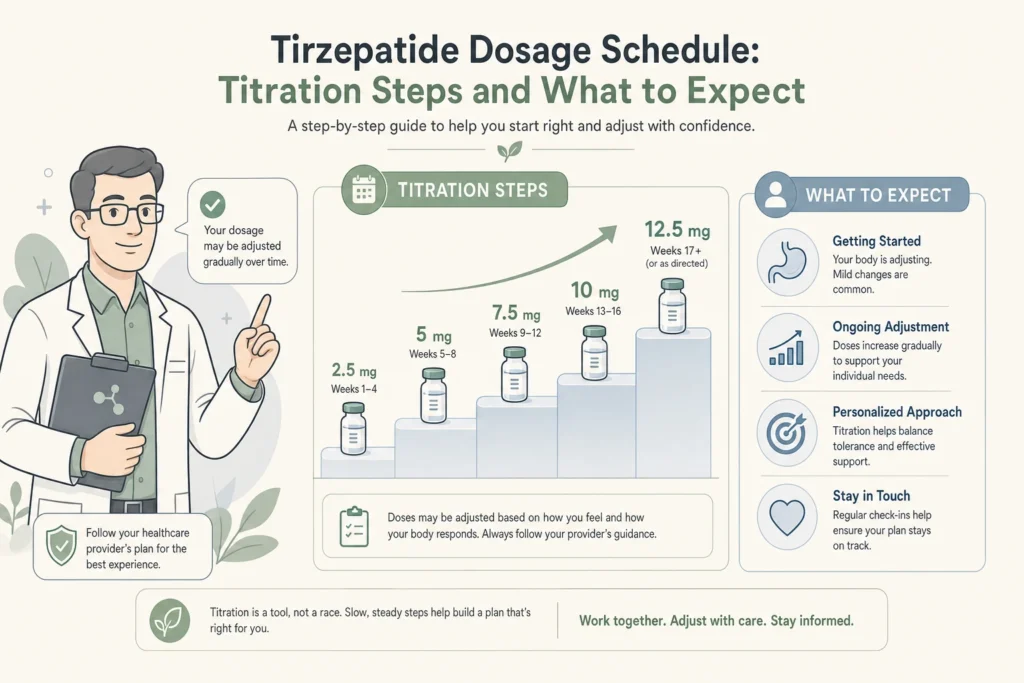
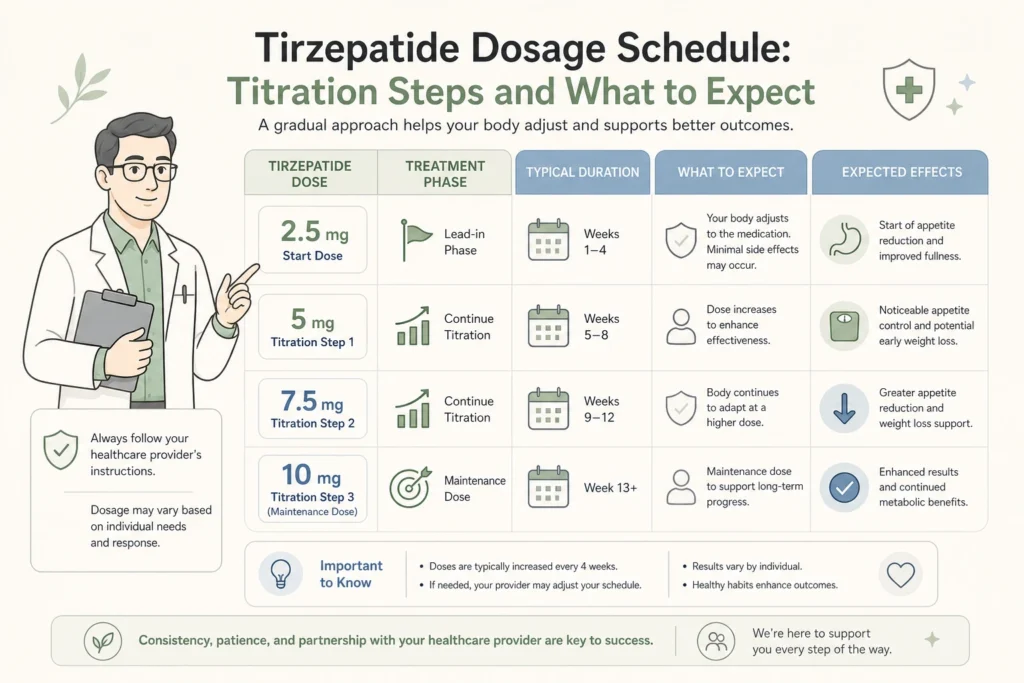
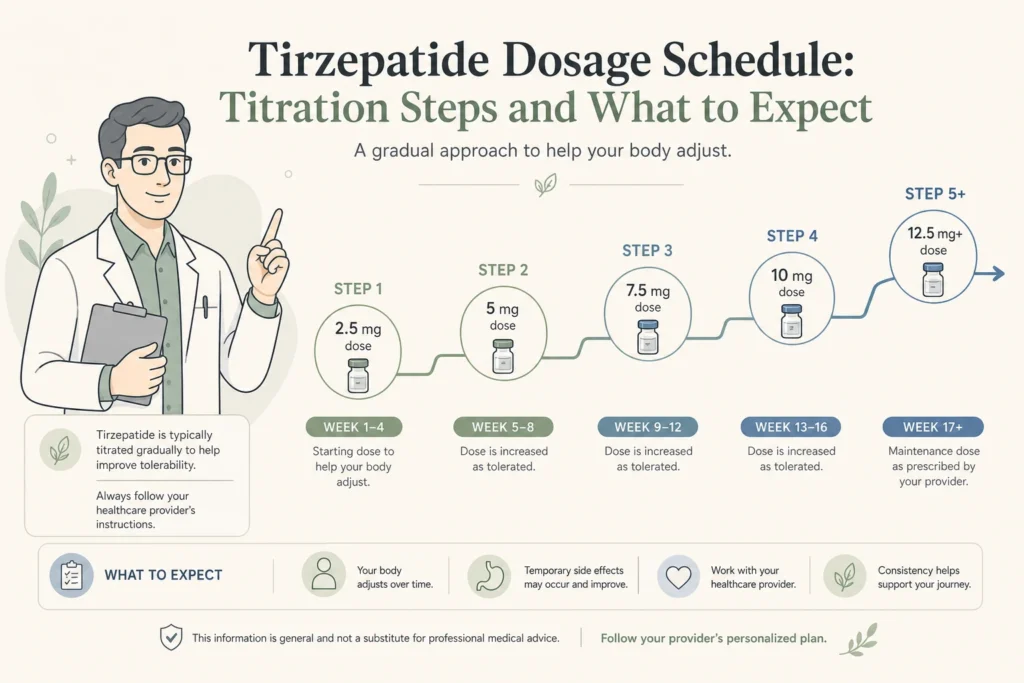
Tirzepatide Dosage Schedule: Titration Steps and What to Expect

Tirzepatide Dosage Schedule: Titration Steps and What to Expect

September 20, 2026

Patients starting tirzepatide often expect the first injection to feel like the start of real treatment. It isn’t. The 2.5 mg starting dose is a lead-in step the label says is not intended to produce weight loss on its own, and plenty of new patients spend a full month wondering why nothing seems to be happening.

Tirzepatide’s titration schedule moves in 2.5 mg increments, from a 2.5 mg starting dose up to a possible maximum of 15 mg, with at least four weeks required between any increase. Unlike some GLP-1 schedules, most of those increases are optional rather than mandatory. Every patient starts the same way, but where they land depends on response and tolerability, not a fixed finish line printed on the label. That’s exactly what Body Works physicians in Nolensville, TN and Franklin, TN reassess at every follow-up, comparing weight trend and side effects against the current dose before ever discussing the next one.

Illustration of Tirzepatide Dosage Schedule: Titration Steps and What to Expect in a modern medical wellness setting

The Full Tirzepatide Titration Ladder

Tirzepatide has six possible dose levels between the starting point and the labeled maximum, but only the first increase is fixed on the label. Everything after 5 mg is an “if needed” decision a prescriber makes based on how much additional weight reduction or glycemic control the current dose is still producing.

StepEarliest weekDoseStatus
112.5 mg weeklyLead-in dose, not intended to be therapeutic
255 mg weeklyFirst dose with a treatment effect
397.5 mg weeklyOptional increase
41310 mg weeklyOptional increase
51712.5 mg weeklyOptional increase
62115 mg weeklyMaximum labeled dose

These steps come from the FDA-approved prescribing information for tirzepatide, which requires at least four weeks at a dose before any further increase. A prescriber sets your actual pace and ceiling based on your response and tolerability, not this table.

Why Is 5 mg the First Dose That Actually Treats Anything?

The 2.5 mg starting dose exists purely to reduce nausea and vomiting before the drug’s real GIP and GLP-1 effects begin at 5 mg. Tirzepatide is a dual agonist, meaning it activates two gut hormone receptors instead of one, and the combined effect on appetite and gastric emptying is stronger than semaglutide’s at a comparable point in titration.

That extra strength is also why the lead-in step exists at all. Starting straight at 5 mg produces far more gastrointestinal side effects in most patients than easing in at half that dose for a month first. The FDA label reports constipation in 17% of patients at the 5 mg dose, 14% at 10 mg, and 11% at 15 mg, against 5% on placebo, a rate that actually trends down at higher doses once the body has adapted through the lower steps. Four weeks is enough time for the gut to adjust before the medication is asked to do its actual job.

Supporting illustration for Tirzepatide Dosage Schedule: Titration Steps and What to Expect in a modern medical wellness setting

Do Most Patients Reach the Maximum 15 mg Dose?

No. Many patients plateau their titration well below 15 mg once their weight loss and appetite control are meeting goals, because higher doses do not automatically mean better results for every patient, only the option of them. In the SURMOUNT-1 trial published in the New England Journal of Medicine, the three tested maintenance doses, 5 mg, 10 mg, and 15 mg, produced average weight reductions of 16.0%, 21.4%, and 22.5% respectively at 72 weeks, meaningful results at every level tested, not just the top one.

A prescriber who keeps a patient at 10 mg instead of pushing toward 15 mg isn’t underdosing them. If the current dose is producing steady progress with tolerable side effects, there’s often no clinical reason to climb further. Increases are meant to answer a specific question, is more dose needed, not to fill out the highest number on the label.
Supporting illustration for Tirzepatide Dosage Schedule: Titration Steps and What to Expect in a modern medical wellness setting

How Does This Compare to Semaglutide's Schedule?

Semaglutide’s titration is more rigid: five fixed steps from 0.25 mg to a single 2.4 mg maintenance dose, each held for four weeks regardless of response, as laid out in the FDA-approved prescribing information for semaglutide. Tirzepatide’s ladder has more optional stops but also more room to stay at a lower, better-tolerated dose if it’s already working. In the STEP 1 trial, semaglutide’s maintenance dose produced 14.9% average weight loss at 68 weeks, below tirzepatide’s dual-hormone effect at comparable doses.

Neither schedule is objectively faster since both take roughly four months minimum to reach a standard treatment dose. The choice between them usually comes down to how a patient’s body responds to each mechanism, not the calendar. In the STEP 1 trial published in the New England Journal of Medicine, semaglutide patients kept losing weight through the full 68-week study, and tirzepatide showed the same pattern through 72 weeks in SURMOUNT-1, so neither medication’s titration schedule is really about speed. It’s about finding the dose your body tolerates well enough to sustain long-term treatment. Our full semaglutide dosage schedule guide lays out that comparison in detail, and both medications are available through physician-supervised programs at tirzepatide therapy and semaglutide therapy.

What Should You Watch for at Each Increase?

Nausea, reduced appetite, and occasional constipation tend to reappear briefly after every dose increase, then settle within a week or two, a pattern that repeats at each of the six steps. That repeating pattern is normal and expected. What isn’t normal is severe abdominal pain, persistent vomiting, or an inability to keep fluids down, all of which warrant a same-day call to your prescriber rather than waiting it out. A full breakdown of what’s typical at each week of treatment, and what counts as a red flag, is in our guide to GLP-1 side effects by week.
Injection technique matters more as the dose climbs. According to the tirzepatide injection instructions published by MedlinePlus, the medication is injected into the abdomen, thigh, or upper arm, and the site should rotate with every dose. The same source notes that a missed dose can still be taken up to four days late. Beyond that window, skip it and resume the normal weekly schedule rather than doubling up. That full process, including what changes at higher doses, is covered in how to inject semaglutide and tirzepatide. For a deeper look at what results typically look like at each dose level, see our tirzepatide deep dive on dosing and results.
The most common question our clinical team hears during a tirzepatide follow-up isn’t “when do I go up,” it’s “do I need to.” That’s a deliberate shift from how most patients expect titration to work, and it’s why Body Works reviews weight trend, appetite control, and side effects at every visit before deciding whether the next step is worth taking.

Whether you’re about to start tirzepatide or you’re mid-titration and unsure whether to increase, our physician-supervised teams in Franklin and Nolensville build the ladder around your response, not a fixed chart. Schedule a Free Consultation to get started.

Supporting illustration for Tirzepatide Dosage Schedule: Titration Steps and What to Expect in a modern medical wellness setting

Frequently Asked Questions

Climbing all six steps to 15 mg takes a minimum of 20 weeks, since each increase requires at least four weeks at the current dose. Many patients never reach that point because a lower dose already meets their goals.
Yes. The 2.5 mg starting dose is a lead-in step, not a treatment dose, so minimal appetite or weight change in the first four weeks is expected rather than a sign the medication isn’t working.
Yes, if it’s controlling appetite and producing steady results with tolerable side effects. There’s no requirement to reach 15 mg, and many patients maintain their results at 5 mg or 10 mg indefinitely.
Pricing depends on dose level and program length. Body Works is a cash-pay clinic with payment plans and HSA and FSA eligibility, and a free consultation is where you get an exact figure alongside a personalized titration plan.
Our Nolensville office at Burkitt Commons and our Franklin office on Murfreesboro Road both run physician-supervised tirzepatide programs, including dose titration, lab monitoring, and side-effect management. Patients from Brentwood, Spring Hill, Cool Springs, and across Williamson County use whichever office is closer.

Medically reviewed by Dr. Donald Vollmer, MD
Managing Physician, Body Works TN

Browse Our Blog

Semaglutide Dosage Schedule: How Titration Works Week by Week

Semaglutide Dosage Schedule: How Titration Works Week by Week

September 17, 2026

The dose on a semaglutide prescription rarely matches the dose a patient ends up taking, and that gap confuses people every week. Someone reads that the standard maintenance dose for chronic weight management is 2.4 mg, does the math on how fast they expect results, and then gets handed a pen loaded with roughly a tenth of that amount for the first injection.

Semaglutide starts at 0.25 mg once weekly and reaches the 2.4 mg maintenance dose over about sixteen weeks, climbing through four fixed steps roughly a month apart. The low starting dose isn’t a smaller version of treatment. It’s the same treatment on a schedule built to let the digestive system adjust before the medication does its full job. Body Works providers in Franklin, TN and Nolensville, TN set that schedule at the first visit and then move it around how each patient actually tolerates it, not a fixed calendar.

Illustration of Semaglutide Dosage Schedule: How Titration Works Week by Week in a modern medical wellness setting

The Standard Semaglutide Titration Schedule

The FDA-approved label for semaglutide’s weight management indication lays out five dose levels, each held for four weeks before the next increase, unless a prescriber decides more time is needed. That structure is deliberate: the dose that treats obesity long-term is more than nine times the starting dose, and reaching it in one step would make the early gastrointestinal side effects far worse for most patients.

StepWeeksDosePurpose
11 to 40.25 mg weeklyInitiation, not intended for a weight-loss effect
25 to 80.5 mg weeklyFirst increase
39 to 121 mg weeklyMid-range step
413 to 161.7 mg weeklyPre-maintenance step
517 onward2.4 mg weeklyStandard maintenance dose

These numbers come from the FDA-approved prescribing information for semaglutide. A prescriber sets and adjusts the actual schedule for each patient based on tolerability, response, and medical history, so the table describes the labeled default, not a guarantee of your own timeline.

Why Does the Dose Start Low and Climb So Slowly?

Semaglutide’s most common side effects, nausea, constipation, and diarrhea, are dose related, so a slow climb spreads the adjustment period over months instead of concentrating it in the first week. In the STEP 1 trial published in the New England Journal of Medicine, participants who titrated on this same four-week schedule lost an average of 14.9% of body weight at 68 weeks with a discontinuation rate for gastrointestinal events under 5%.

The mechanism behind the side effects is the same mechanism behind the results: semaglutide slows stomach emptying and quiets appetite signals, and a body adjusting to that gradually tolerates it better than one hit with the full dose at once. Four weeks is roughly how long it takes the gut to adapt to a given dose level before the next step raises the bar again.

Supporting illustration for Semaglutide Dosage Schedule: How Titration Works Week by Week in a modern medical wellness setting

What If You Are Not Ready to Move Up on Schedule?

Staying at a dose for an extra four weeks, or longer, is following the label, not falling behind it. The prescribing information allows a prescriber to hold a patient at any step until side effects are manageable before increasing again, and there is no penalty for taking five or six months to reach maintenance instead of four.

This flexibility matters most in the first two dose levels, where most of the early nausea and appetite change happens. A patient who needs two months at 0.5 mg instead of one isn’t behind. They’re being titrated correctly for their body. What is and is not typical to feel at each step, and which symptoms warrant a same-day call instead of patience, is covered in our guide to GLP-1 side effects by week.

Supporting illustration for Semaglutide Dosage Schedule: How Titration Works Week by Week in a modern medical wellness setting

How Does the Semaglutide Schedule Compare to Tirzepatide's?

Both medications use a four-week step-up pattern, but tirzepatide’s ceiling is higher and its first month is a true lead-in dose rather than a therapeutic one. Semaglutide moves through five doses from 0.25 mg to 2.4 mg. The FDA-approved prescribing information for tirzepatide starts patients at a 2.5 mg dose not intended to produce weight loss on its own, then allows increases in 2.5 mg increments to a maximum of 15 mg, with each step spaced at least four weeks apart.

Neither schedule is faster in absolute terms since both give patients roughly four months to reach a standard maintenance dose, but tirzepatide’s dual GLP-1/GIP mechanism produced larger average weight loss at its top dose in trials, 22.5% of body weight at 72 weeks in the SURMOUNT-1 trial published in the New England Journal of Medicine, compared with semaglutide’s 14.9% at 68 weeks in STEP 1. That gap is why some patients who plateau on semaglutide’s maintenance dose ask about switching rather than simply waiting longer at 2.4 mg. The two drugs are titrated for the same underlying reason, tolerability, even though they are not interchangeable milligram for milligram, and the full step-by-step tirzepatide breakdown is in our tirzepatide dosage schedule guide. Both medications are available through semaglutide therapy and tirzepatide therapy at Body Works.

What Should You Expect Physically While You Titrate?

Most patients feel the strongest appetite and digestive effects in the first week after each dose increase, then notice them settle before the next step. According to the semaglutide injection instructions published by MedlinePlus, the medication should be injected on the same day each week in the upper arm, thigh, or stomach area, rotating the site with every dose to reduce irritation at any one spot.

Appetite reduction is usually the first thing patients notice, often within the first two weeks, well before the scale reflects much change. Weight loss then tends to accelerate as the dose climbs through the middle steps. For a realistic week-by-week and month-by-month picture of when results actually show up, see our semaglutide results timeline. Injection technique itself, including site rotation and what to do about a missed dose, is covered in how to inject semaglutide and tirzepatide.

Since 2022, Body Works providers in Franklin and Nolensville have built semaglutide titration schedules around the patient in front of them rather than a printed chart, adjusting pace when nausea runs longer than expected or holding a dose when lab work suggests waiting. That’s the part of the FDA label a chart can’t show: which of the five steps needs to move slower for a specific person, and how to tell the difference between an expected adjustment and a symptom that needs medical attention.

Once semaglutide reaches its maintenance dose, most patients stay there for the rest of active treatment, occasionally stepping back down if side effects reappear. Our guide to GLP-1 microdosing and maintenance covers what changes after titration ends.

Whether you are about to start semaglutide or you are partway through titration and want a second opinion on your pace, our physician-supervised teams in Franklin and Nolensville build the schedule around your labs, your history, and how your body is actually responding. Schedule a Free Consultation to get started.

Supporting illustration for Semaglutide Dosage Schedule: How Titration Works Week by Week in a modern medical wellness setting

Frequently Asked Questions

The labeled schedule reaches the 2.4 mg maintenance dose at week 17, about four months after the first injection. Many patients take longer because a prescriber holds them at a lower dose to manage side effects, and that extension does not change the eventual outcome.
No. Jumping doses increases the risk of severe nausea, vomiting, and dehydration, and it is not how the medication was studied or approved. Every increase should come from your prescriber based on how you tolerated the current dose, not a self-adjusted schedule.
That is expected. The 0.25 mg starting dose isn’t intended to produce meaningful weight loss on its own. Its job is tolerability, not results. Appetite and weight changes typically become noticeable once you reach the 0.5 mg or 1 mg steps.
Pricing depends on the dose level and the length of the program. Body Works is a cash-pay clinic offering payment plans and HSA and FSA eligibility, and a free consultation is where you get an exact figure alongside your personalized titration plan.
Our Franklin office on Murfreesboro Road and our Nolensville office at Burkitt Commons both run physician-supervised semaglutide programs, including dose titration, lab monitoring, and side-effect management. Patients from Brentwood, Spring Hill, Cool Springs, and across Williamson County use whichever office is closer.

Medically reviewed by Dr. Donald Vollmer, MD
Managing Physician, Body Works TN

Browse Our Blog

Switching From Tirzepatide to Retatrutide: What Changes

Switching From Tirzepatide to Retatrutide: What Changes

September 13, 2026

You reached 15 mg. The scale that dropped two pounds a week for eight months has been flat since spring, and the weekly shot now feels like maintenance you did not sign up for. Then a friend mentions the “GLP-3,” and the question writes itself: is switching from tirzepatide to retatrutide the next step, or a mistake you pay for in nausea?

Switching from tirzepatide to retatrutide is a supervised change in medication, not an upgrade you can dose your way into. Retatrutide, the medication people call a GLP-3, adds a third receptor that tirzepatide does not touch, and in its 48-week phase 2 trial the top dose produced 24.2% average weight loss, ahead of the 20.9% tirzepatide reached in its own 72-week trial. The switch works best for people who have stalled at a stable tirzepatide dose, and it is timed to the weekly schedule you already keep, with retatrutide started low and raised on its own ladder rather than matched milligram for milligram.

Body Works manages semaglutide, tirzepatide, and retatrutide (GLP-3) patients under physician supervision in Franklin, TN and Nolensville, TN. Here is what the switch involves and how the first eight weeks tend to go.

Illustration of Switching From Tirzepatide to Retatrutide: What Changes in a modern medical wellness setting

Why Do People Switch From Tirzepatide to Retatrutide?

Because they have stopped losing weight on tirzepatide, or because they want the extra mechanism retatrutide adds. Tirzepatide acts on two receptors, GIP and GLP-1, which together reduce appetite and slow stomach emptying. Retatrutide acts on those two plus the glucagon receptor, and glucagon activity is associated with higher energy expenditure. Tirzepatide mostly changes how much you eat, and retatrutide is designed to change both how much you eat and how much you burn.

The trial numbers are the reason the question keeps coming up. In the SURMOUNT-1 trial of tirzepatide in the New England Journal of Medicine, participants on 15 mg lost 20.9% of their body weight over 72 weeks. In the phase 2 retatrutide trial in the same journal, participants on 12 mg lost 24.2% in 48 weeks, and every participant at 8 mg or 12 mg lost at least 5%. Those are separate trials with different lengths and populations, so the gap is a tendency, not a measured head-to-head result. The direct comparison, a phase 3 study of retatrutide against tirzepatide in adults with obesity, is registered on ClinicalTrials.gov as NCT06662383 and is active but not yet reporting.

A plateau is the most common trigger in practice. Weight loss on any GLP-1 medication slows as the body settles at a new set point, and a stable weight for three months at the highest dose you tolerate is a reasonable point to ask about the next option.

How Does Retatrutide Differ From Tirzepatide?

Three receptors instead of two, a different dose ladder, and a weight-loss ceiling that appears to sit higher. Both are once-weekly injections. Both are titrated slowly because gastrointestinal side effects cluster around dose increases. The practical differences are in the table.

FactorTirzepatideRetatrutide (GLP-3)
ReceptorsGIP and GLP-1GIP, GLP-1, and glucagon
Trial doses5, 10, and 15 mg weeklyPhase 2: 1, 4, 8, and 12 mg weekly. Phase 3 (type 2 diabetes): 4, 9, and 12 mg
Starting dose in trials2.5 mg, raised by 2.5 mg no faster than every 4 weeks2 mg or 4 mg, raised toward the target dose
Weight loss at top dose20.9% at 72 weeks (SURMOUNT-1)24.2% at 48 weeks (phase 2)
Main side effectsNausea, diarrhea, constipation, mostly during escalationSame pattern, dose-related, reduced by a 2 mg start
Regulatory statusFDA approved for chronic weight managementPhase 3 under way. First results published 2026

The phase 3 program has started to report. The TRANSCEND-T2D-1 trial published in The Lancet in June 2026 gave retatrutide 4 mg, 9 mg, or 12 mg to 537 adults with type 2 diabetes for 40 weeks. Body weight fell 11.5%, 13.9%, and 15.3% respectively against 2.6% on placebo, and the gastrointestinal side effects were mostly mild to moderate and subsided over time. Only 2% to 5% of participants stopped because of side effects.

The three-way comparison with semaglutide and the explainer on why retatrutide is nicknamed GLP-3 go deeper.

When Is the Right Time to Switch?

After you have reached a stable tirzepatide dose and held it long enough to know what it does for you. Switching in the middle of the tirzepatide ladder gives up information: you do not yet know whether 12.5 mg or 15 mg would have restarted the loss. Three signals make the switch worth discussing.

  • A true plateau. Weight has been flat for roughly three months at the highest tirzepatide dose you can tolerate, with your eating and activity unchanged.
  • A goal tirzepatide is unlikely to reach. In SURMOUNT-1, 57% of participants on 15 mg lost 20% or more of their body weight at 72 weeks, which means 43% did not. If you have lost 15% and your provider agrees another 10% is realistic and medically appropriate, the higher ceiling in the retatrutide data becomes the deciding factor.
  • Side effects you cannot get past. Some patients cannot climb the tirzepatide ladder without persistent nausea. Retatrutide is not automatically gentler, but its trials showed that starting at 2 mg rather than 4 mg partially mitigated stomach side effects, which gives a supervised switch a slower on-ramp to try.

If tirzepatide is still working, the honest advice is to stay on it. And if the plateau traces to something fixable, such as protein intake that has drifted below target or a dose that was never fully raised, that gets addressed first. The tirzepatide dosing and results guide walks through what the full ladder should have delivered before a plateau is called.

Supporting illustration for Switching From Tirzepatide to Retatrutide: What Changes in a modern medical wellness setting

How Is the Switch Timed, and Do You Need a Washout?

No washout period is built into the switch. Retatrutide replaces tirzepatide on the next scheduled injection day. Tirzepatide has a half-life of approximately 5 days according to its FDA prescribing information, which is why it is dosed weekly and why the label allows a missed dose to be taken within 4 days. By the time your next weekly injection comes due, the previous tirzepatide dose is already declining. Taking the first retatrutide dose on that same day keeps the weekly rhythm and avoids a gap in appetite control.

The dose starts over rather than converting. There is no published table that maps 15 mg of tirzepatide onto a retatrutide dose, and the two molecules are not interchangeable at the receptor level. Retatrutide begins at the low end of its own ladder regardless of how high your tirzepatide dose was, because the glucagon activity is new to your body, and the phase 2 investigators reported that a 2 mg start, compared with 4 mg, partially mitigated the stomach side effects. Anyone who tells you to “match the milligrams” is guessing.

Two things carry over unchanged from your tirzepatide plan. Protein stays at target, because a 2025 joint nutrition advisory from four medical societies recommends 1.2 to 1.6 grams per kilogram per day during medication-driven weight loss to protect lean mass, and a second round of rapid loss raises the stakes. And resistance training continues, for the same reason. The guide to preventing muscle loss on GLP-1 medications covers the plan.

What Should You Expect in the First Eight Weeks?

A return of the early-titration feeling, then a new drop in weight. The first weeks on retatrutide look like the first weeks on tirzepatide did: appetite falls further, meals get smaller, and stomach symptoms show up around each dose increase and fade before the next. In the 48-week phase 2 trial the side effects were dose-related, mostly mild to moderate, and the 2 mg starting dose eased them. One effect is specific to retatrutide: a dose-dependent increase in resting heart rate that peaked at 24 weeks and declined afterward. Your provider will track it.

The weight response arrives in stages. Across the phase 2 dose groups, participants had lost 7.2% to 17.5% by week 24 and 8.7% to 24.2% by week 48, with the higher doses pulling away over time. The first month tells you little, because the curve is still steep at week 24. Constipation is worth planning for from the first injection, because slower stomach emptying plus smaller meals is the setup for it, and the fiber, protein, and fluid plan for GLP-1 constipation applies to retatrutide without changes.

Call your provider the same day for persistent vomiting, dehydration, severe upper abdominal pain, or a racing heart at rest. Those symptoms change the plan.

Supporting illustration for Switching From Tirzepatide to Retatrutide: What Changes in a modern medical wellness setting

Who Should Not Switch to Retatrutide?

Anyone for whom tirzepatide is still doing its job, anyone who is pregnant or planning pregnancy, and anyone with the conditions that already ruled out tirzepatide. The tirzepatide label carries a boxed warning for people with a personal or family history of medullary thyroid carcinoma or Multiple Endocrine Neoplasia syndrome type 2, and a history of pancreatitis calls for caution. Retatrutide shares the GLP-1 pathway and the same precautions apply until its own label says otherwise.

The phase 3 trials excluded certain groups, and a supervised clinic follows the same logic: the switch is for adults who have finished a proper tirzepatide course with current bloodwork and a reason that holds up in a consultation. A patient who wants retatrutide because it is newer, with weight still coming off on tirzepatide, does not need it yet.

Supporting illustration for Switching From Tirzepatide to Retatrutide: What Changes in a modern medical wellness setting

Switching From Tirzepatide to Retatrutide in Franklin and Nolensville

In 2025, Body Works guided more than 130 patients through its medical weight loss program at the Nolensville office alone. Every patient starting a GLP-1 medication there leaves the first visit with written nutrition and symptom guidance, and when a patient reports a problem the team looks at two things first: what they have been eating and drinking, and when the change began relative to the last dose increase. Bring the same two facts to a plateau conversation, your dose history and a week of meals, because they sort the plateaus that need a medication change from the ones that need a protein correction or a final dose step. That sorting happens before any retatrutide is discussed.

If you have stalled on tirzepatide and want to know whether retatrutide (GLP-3) is the right next step, the Franklin and Nolensville teams can review your history and build the plan. Schedule a Free Consultation to get started, or read about the retatrutide program at Body Works and the broader medical weight loss program.

Our full medical weight loss program is available at both the weight loss clinic in Franklin and weight loss clinic in Nolensville.

Frequently Asked Questions

Yes, under physician supervision. Retatrutide replaces tirzepatide on the next scheduled weekly injection day, and it starts at the low end of its own dose ladder rather than at a dose matched to your tirzepatide dose. No washout period is required because tirzepatide’s 5-day half-life means the prior dose is already declining by the next injection day.
The trial data point that way. Retatrutide’s top phase 2 dose produced 24.2% weight loss at 48 weeks, versus 20.9% for tirzepatide’s top dose at 72 weeks in SURMOUNT-1. Those are separate trials, and the head-to-head phase 3 study registered as NCT06662383 has not reported yet, so the difference is a tendency until it does.
On the next scheduled injection day, about seven days after your last tirzepatide dose. There is no benefit to a longer gap, and a gap of several weeks brings appetite back before the new medication takes over. The switch keeps the weekly rhythm you already have.
Pricing depends on the medication, the dose, and the plan you choose, and the free consultation is where you get the exact figure along with your titration schedule. Body Works is a cash-pay clinic with payment plans and HSA and FSA eligibility, and the review of whether a switch is warranted is part of the visit.
The Franklin office on Murfreesboro Road and the Nolensville office at Burkitt Commons both manage retatrutide (GLP-3) and tirzepatide patients under physician supervision, including the timing of a switch and the new dose ladder. Patients from Brentwood, Spring Hill, Cool Springs, and across Williamson County use whichever location is closer.

Medically reviewed by Dr. Donald Vollmer, MD
Managing Physician, Body Works TN

Browse Our Blog

See Body Works first in your Google results.

Add as a preferred source on Google