Ipamorelin vs Sermorelin vs Tesamorelin: Which Growth Hormone Peptide Fits Your Goal
October 6, 2026
All three of these show up in the same conversation, usually because someone read that they all “boost growth hormone” and assumed that made them interchangeable. They are not. Ipamorelin, sermorelin, and tesamorelin raise growth hormone through three different mechanisms, and the one worth choosing depends entirely on what problem you are trying to solve.
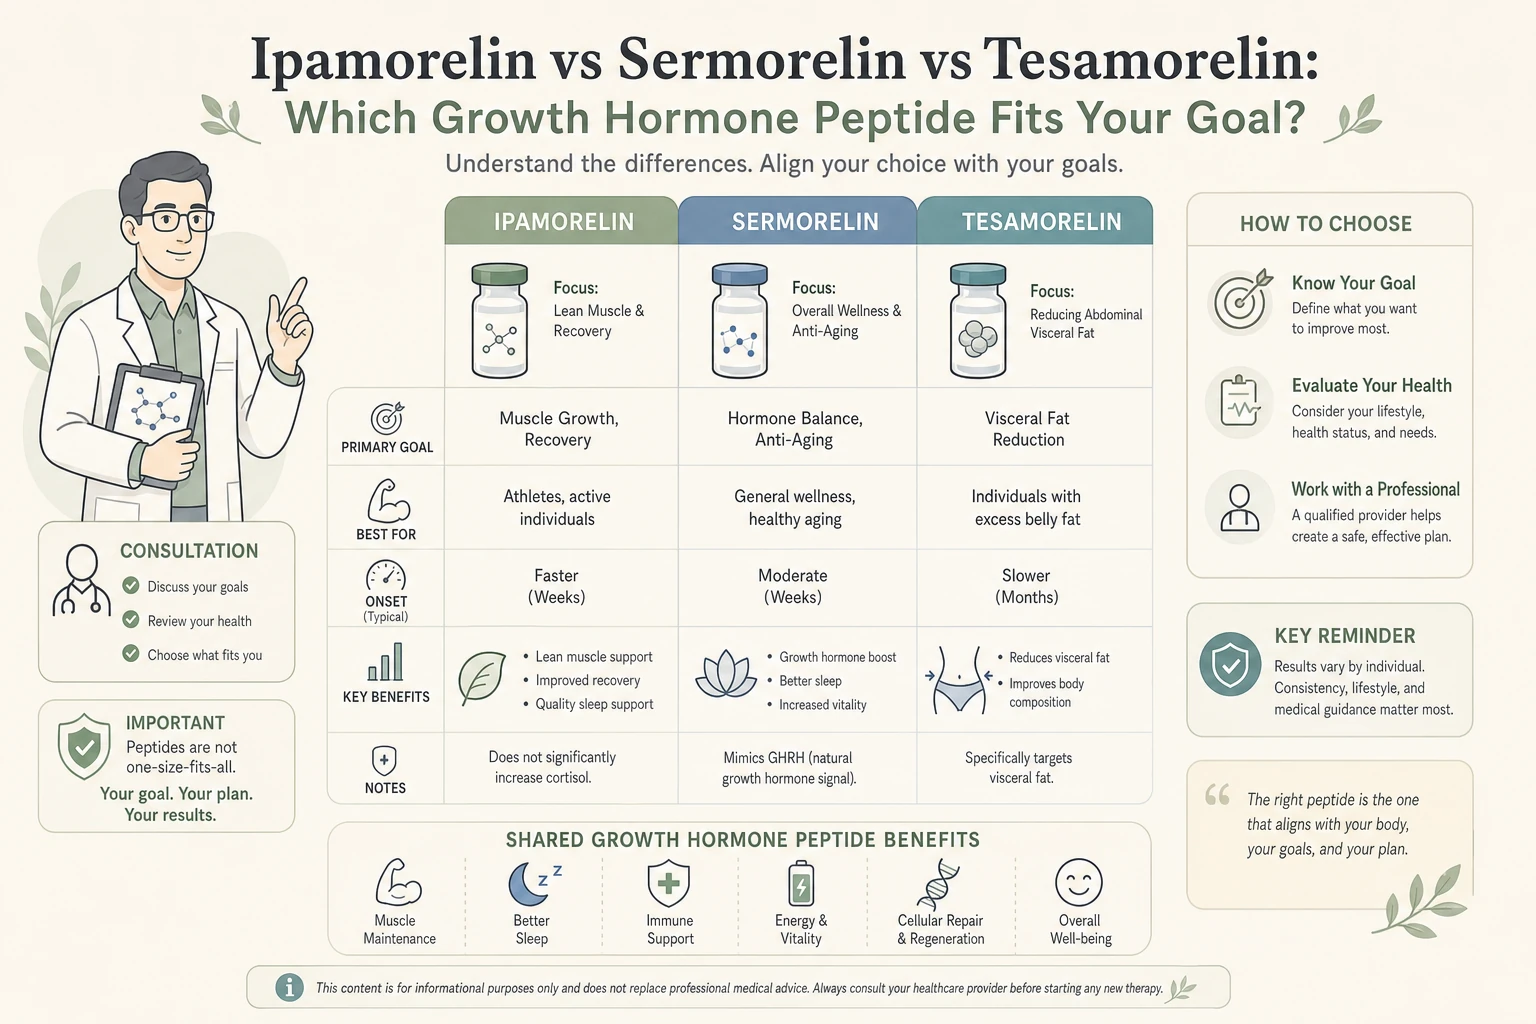
Sermorelin is a growth hormone-releasing hormone analog that stimulates the pituitary’s natural, pulsatile release pattern and has the longest clinical track record of the three. Ipamorelin is a selective ghrelin receptor agonist that triggers growth hormone release without raising cortisol or other hormones, making it the gentlest option on paper. Tesamorelin is a stabilized, more potent GHRH analog with the strongest clinical trial evidence, concentrated specifically in visceral fat reduction. None of the three is simply a stronger or weaker version of the others; they are built differently, on purpose.
Body Works offers physician-supervised protocols for all three at its Nolensville, TN and Franklin, TN offices. Here is what separates them and how a provider matches one to your goal.
What Do Ipamorelin, Sermorelin, and Tesamorelin Have in Common?
All three increase growth hormone output from the pituitary gland, and all three are given as subcutaneous injections rather than pills, because growth hormone-axis peptides do not survive oral digestion intact. Beyond that, the similarities mostly end. Each targets a different receptor system, has a different depth of clinical trial evidence behind it, and is reasonably matched to a different goal, general wellness and sleep quality, a more selective and minimal-side-effect release pattern, or measurable visceral fat reduction.
How Does Sermorelin Work?
Sermorelin is a synthetic 29-amino-acid fragment of growth hormone-releasing hormone that retains the full biological activity of the much larger natural hormone. It binds the GHRH receptor on pituitary cells and stimulates the gland’s own pulsatile release pattern, rather than flooding the body with growth hormone directly, which is part of why it is considered a more physiologic approach than direct growth hormone injections. A published clinical review of sermorelin’s use in diagnosing and treating growth hormone deficiency documented its efficacy and safety profile across a substantial clinical trial history, the deepest evidence base of the three peptides discussed here, even though its original approved use was for growth hormone deficiency rather than general wellness.
How Does Ipamorelin Work, and How Is It Different From Sermorelin?
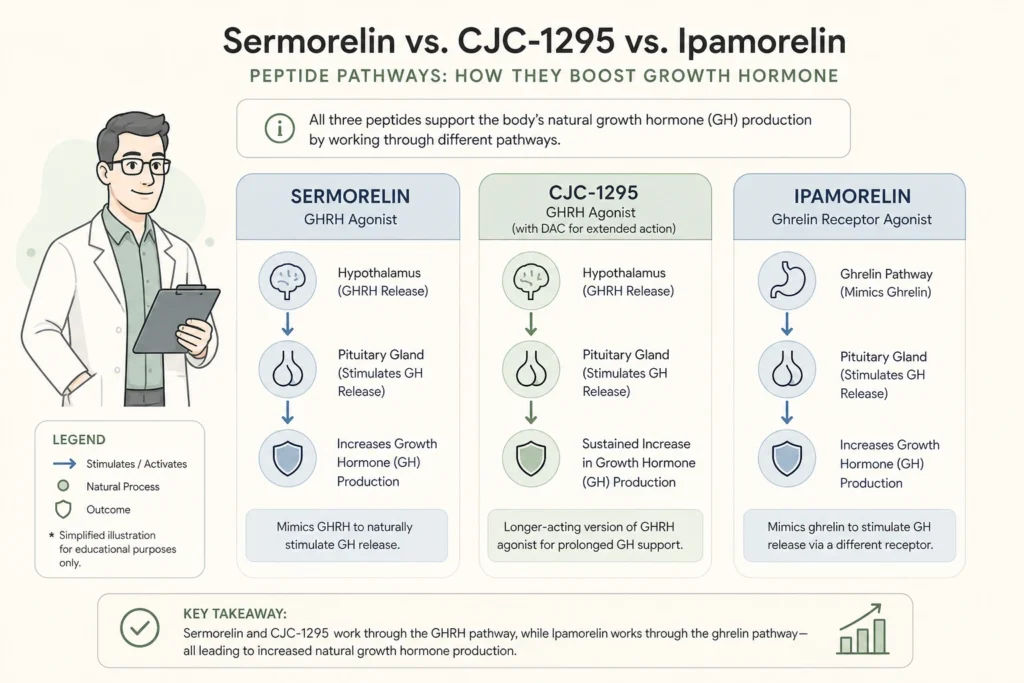
Ipamorelin works through an entirely different receptor: it is a selective agonist of the ghrelin receptor, which also drives growth hormone release, but through a separate signaling pathway than GHRH does. The original research describing ipamorelin found that it stimulated growth hormone release without meaningfully increasing cortisol, prolactin, or other pituitary hormones, even at doses far above what was needed for its growth hormone effect. That selectivity is the entire reason ipamorelin has the reputation it does: older ghrelin-receptor peptides in the same family raised cortisol and prolactin alongside growth hormone, and ipamorelin was specifically developed to avoid that.
A broader review of growth hormone secretagogues in the management of body composition in hypogonadal men noted that adverse effects with ipamorelin were rare and comparable to sermorelin’s safety record, which is a meaningful finding since it means the selectivity does not come at the cost of a worse safety record.
How Does Tesamorelin Work, and Why Is It Studied for Visceral Fat?
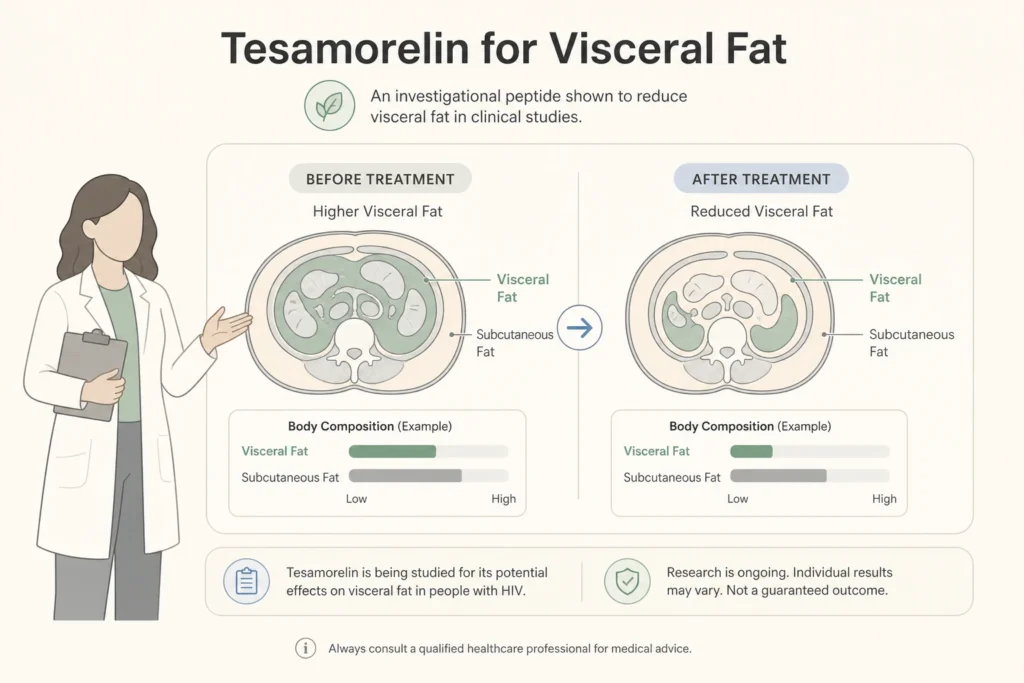
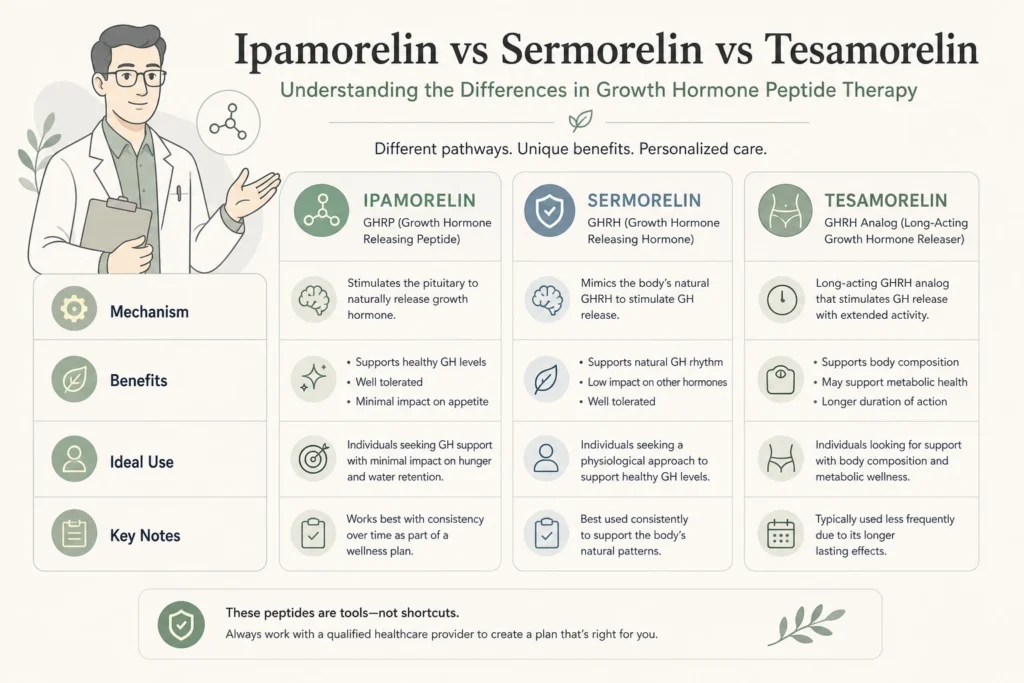
Tesamorelin is a stabilized synthetic GHRH analog, more potent and longer-acting than sermorelin, that binds the same GHRH receptor but produces a stronger and more sustained growth hormone response. It has the most rigorous clinical trial record of the three, built around a specific outcome: visceral fat reduction. A post hoc analysis of a phase 3 placebo-controlled trial found that tesamorelin produced a measurable and consistent reduction in visceral adipose tissue across the study population, and a more recent analysis in patients on modern antiretroviral regimens confirmed tesamorelin maintained both efficacy and a favorable safety profile in that population. The trial evidence behind tesamorelin is specifically about visceral fat, the metabolically active fat around internal organs, not general body composition or growth hormone deficiency the way sermorelin’s evidence is.
| Factor | Sermorelin | Ipamorelin | Tesamorelin |
|---|---|---|---|
| Receptor target | GHRH receptor | Ghrelin receptor | GHRH receptor |
| Best-matched goal | General wellness, sleep, natural GH rhythm | Minimal side-effect selective GH release | Visceral fat reduction |
| Potency | Moderate | Moderate | Higher, longer-acting |
| Effect on other hormones | Minimal at typical use | Minimal; does not raise cortisol or prolactin | Minimal at typical use |
| Depth of clinical trial evidence | Extensive, decades of use | Moderate, strong mechanism data | Most rigorous, phase 3 trial data |
Can Ipamorelin, Sermorelin, or Tesamorelin Be Combined?
Ipamorelin is frequently paired with CJC-1295, a longer-acting GHRH analog, rather than with sermorelin or tesamorelin, since combining two peptides that hit the same receptor rarely adds meaningful benefit over using the stronger one alone. The detailed comparison of sermorelin against the CJC-1295 and ipamorelin combination covers that specific pairing decision in more depth than fits here. Tesamorelin, because its evidence is built around a specific outcome, visceral fat, is more commonly used on its own for that goal rather than added into a combination protocol. A provider reviewing your goals and bloodwork is the right way to decide whether a combination makes sense for you, rather than assuming more peptides automatically means a better result.

Which One Should You Choose?
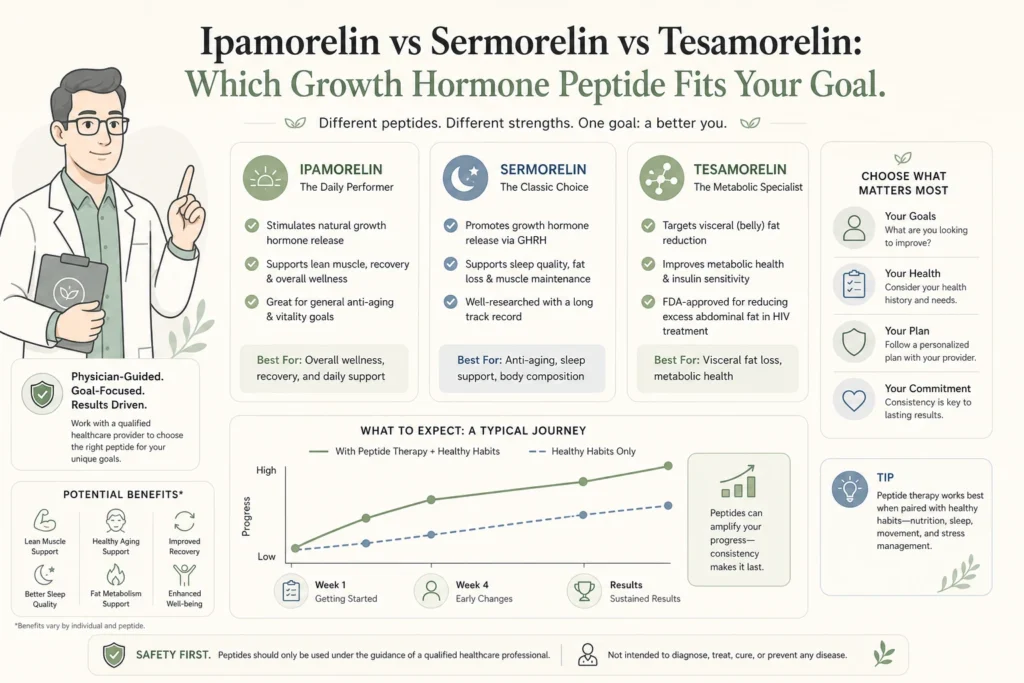
Start with the goal, not the peptide. If general wellness, sleep quality, and a natural growth hormone rhythm are the priority, sermorelin’s long track record makes it the reasonable starting point. If minimizing any effect on cortisol or prolactin matters most, ipamorelin’s selectivity is the differentiator. If the specific concern is visceral fat, the fat that sits around organs and is linked to metabolic risk, tesamorelin has the strongest clinical trial evidence behind that particular outcome. A physician reviewing bloodwork, goals, and health history is the appropriate way to make this decision, not a forum thread comparing anecdotal results.
Growth Hormone Peptides in Nolensville, TN
The question the Nolensville team hears most often is not “which peptide is strongest,” it is “which one actually matches what I’m dealing with.” A patient asking about sleep and general energy gets steered toward a different conversation than one whose bloodwork shows high visceral fat markers, and that goal-first approach is why the team asks about labs and history before naming a peptide at all. Sorting the goal from the peptide first is what keeps the recommendation from defaulting to whichever option is most talked about online that month.
If you want a physician to review your goals and match them to sermorelin, ipamorelin, or tesamorelin, rather than guessing based on what sounds most popular, the Nolensville and Franklin teams can help. Schedule a Free Consultation to get started, or read more about tesamorelin’s specific evidence for visceral fat.
Frequently Asked Questions
Medically reviewed by Dr. Donald Vollmer, MD
Managing Physician, Body Works TN
Browse Our Blog

Testosterone Replacement Therapy in Franklin and Nolensville: What Physician-Supervised Treatment Looks Like
A lot of what passes for testosterone replacement therapy in Franklin, TN and nationwide in 2026 is a questionnaire, a card swipe, and a prescription
GLP-1 Side Effects by Week: What Is Normal, What Passes, What to Report
A symptom that is completely normal in week two can be a reason to call your prescriber in week fourteen. Nausea right after a dose

Ipamorelin vs Sermorelin vs Tesamorelin: Which Growth Hormone Peptide Fits Your Goal
All three of these show up in the same conversation, usually because someone read that they all “boost growth hormone” and assumed that made them

GLP-1 Nausea and Stomach Issues: What Actually Helps
GLP-1 nausea affects 44% of semaglutide patients and 25% to 29% on tirzepatide, clusters around dose increases, and fades within weeks for most. Smaller meals,
Semaglutide in Nolensville, TN: Availability and How to Start
Searching for semaglutide in a town the size of Nolensville turns up a strange gap: national telehealth ads everywhere, but almost nothing about a real

Semaglutide in Franklin, TN: Availability and How to Start
If you have been researching semaglutide for weight loss, you have probably hit the same wall everyone else does: a telehealth app that ships a